
The Facility Is the Easy Part — Reshoring Peptide Manufacturing Fails on the People-and-Process Layer
The binding constraint on reshoring peptide manufacturing is not capital. It is the qualified-personnel and transfer-discipline layer that turns a building into released batches. Peptide CDMO capital commitments passed $3 billion across 2024 chuig 2026 (Peptidestaff, peptide CDMO capacity expansion tracking, 2026), yet the existing US and European peptide manufacturing workforce is already fully employed, and announced capacity can only be operationalized as fast as qualified people can be hired, onboarded and trained (Peptidestaff reshoring analysis, 2026, a vendor-adjacent publisher). Massachusetts biomanufacturing employment fell 1.5% in 2024, its second straight annual decline (MassBio snapshot via BioSpace, 2025), a single-state figure, not a national supply-and-demand measure.
One qualifier belongs here: no verifiable 2026 statistical workforce-shortage number appears in the retrieved evidence. The shortage case is directional, built from employment trend data and named scarce roles rather than from a measured national gap. Treat it as a criterion for evaluating a domestic partner, not as a settled statistic.
The Conventional View: Reshoring Is a Capital Problem, and Capital Is Being Spent
Sintéis Peptide That mainstream position is straightforward: reshoring peptide manufacturing is a facility-investment and supply-chain-resilience problem, and the money is already moving. Bachem’s Vision 2025–2030 committed CHF 1.2 billion across four sites, with an extra $120 million for sterile fill-finish at King of Prussia, while PolyPeptide’s Malmö expansion completed in Q1 2026 added eight SPPS reactors with roughly 4,000 litres of combined working volume, alongside a $180 million Ambernath expansion announced in April 2026 (Peptidestaff, 2026). On that trajectory, North American peptide API capacity is projected to move from about 18% of global capacity in 2024 to about 28% by 2029, a forecast derived from announced investments rather than audited capacity (Peptidestaff, 2026).
The view is popular because it is measurable, fundable and politically legible. It also has a real origin: the FDA’s analysis of 163 drugs that entered shortage between 2013 and 2017 found quality problems responsible 62 percent of the time (FDA CDER congressional testimony, 2019). A decade of supply-concentration risk followed, and capital is the visible answer. It is also genuinely necessary.

Why the Capital-Only View Breaks Down: Three Specific Failures
Capital builds capacity. Only qualified people and complete process knowledge produce qualified output, and that is where reshoring peptide manufacturing actually stalls.
The first failure is the transfer package itself. Global Biotech Laboratories names incomplete packages, those missing critical process parameters, undocumented known issues or unstated specifications, as the most common cause of tech transfer problems. The company sells transfer services, so read the claim with that interest in view.
A frequently repeated figure holds that roughly half of all tech transfers run into quality problems, based on analysis presented at CDMO Live 2025. Treat it as unconfirmed. No sample size, methodology or primary publication accompanies it, so it cannot carry an argument.
The second failure is sequencing. Analytical method transfer comes first, because if the receiving laboratory cannot measure the molecule the same way, nothing downstream is trustworthy (Global Biotech Laboratories).
The third is staffing. Peptidestaff identifies the scarce roles as process chemists with commercial-scale SPPS experience, analytical scientists with peptide API characterization expertise, QA/QC professionals with FDA and EMA GMP documentation experience, and regulatory affairs scientists with peptide CMC filing experience.
All three failures share one cause: the people-and-process layer is funded as an afterthought to the building.
What the Data Actually Shows: The 18–36 Month Conversion Window
The number that matters for reshoring peptide manufacturing is not how much capacity gets announced, but how long that capacity takes to produce qualified lots. One industry analysis estimates an 18–36 month window between a facility coming online and its first released batch, and treats that window as a planning estimate rather than an industry standard (Peptidestaff, 2026).
The sequence inside that window has six stages: capacity announced, facility complete, analytical methods transferred, engineering or demonstration batch, process Peptides sintéiseacha performance qualification, then inspection and approval. Capital funds the first two. The remaining four are people-gated, and they are where the schedule slips.
Documented practice shows how narrow the failure points are. A preparative HPLC method transferred without its fraction-collection window defined, or a lyophilizer cycle transferred without the load configuration it was developed on, will not reproduce at the receiving site. Neither gap shows up in a facility specification sheet. Both require an operator who has run the method and can recognize the deviation.
That reframes the evaluation. Assess a domestic partner on transfer-package completeness and operator qualification evidence, not on cleanroom classification or reactor volume. The cost premium, estimated at 35–65% depending on compound, scale and services (Peptidestaff, 2026), buys capacity. It does not buy the conversion.
What a Complete Transfer Package and Qualified Operator Actually Require
A domestic partner is auditable only when you can name the artifacts. “Quality processes” is not an evaluation criterion; a transfer package, an analytical method transfer record, an operator qualification file, and an IQ/OQ/PQ protocol set are.
The transfer package is the first artifact to request. Global Biotech Laboratories describes its required contents as the synthetic route, conditions, reagents and critical parameters; HPLC and MS release methods with reference standards; specifications for purity, impurity limits, identity and content; and raw-material sources, prior batch records and known risks. Ask for all four blocks in writing before commercial terms are discussed.
Qualification is the second. The FDA Group’s IQ/OQ/PQ guide explains that Installation Qualification confirms installation against manufacturer specifications and prerequisites, including floor space, utilities, environmental conditions, firmware and serial numbers, and the calibration of tools used during IQ. It must follow Design Qualification, its acceptance criteria must be measurable, and its required outputs are the IQ Protocol, IQ Checklist and IQ Report. Major maintenance, modification, or a routine QA cycle triggers requalification. Everyone executing the protocol must be trained on the equipment and on documentation practices, which is where equipment qualification IQ OQ PQ stops being a paperwork exercise.
Operator qualification is the third, and it is the one buyers most often accept on faith. 21 CFR 211.25(a) requires that each person engaged in the manufacture, processing, packing, or holding of a drug product have the education, training, and experience, or any combination, to enable that person to perform the assigned functions. That is role-specific and function-enabling, not attendance-based: documented evidence and verified understanding are expected, and training must be repeated as procedures change. Assryro’s GMP training guide places that requirement inside a wider regime that draws on 21 CFR 211.34 for consultants, 21 CFR Part 11 for electronic training systems and LMS records, ICH Q10 for competency management within the pharmaceutical quality system, EU GMP Annex 11 for computerized systems, and the FDA’s 2011 process validation guidance on operator training verification.
Three distinctions decide whether a partner has actually done this work. Process transfer moves the synthetic route and its critical parameters; analytical transfer moves the methods, reference standards and specifications, and the two fail independently. General GMP training covers the plant; process-train-specific qualification covers the operator running your route on your equipment. Calibration keeps an instrument reading true; qualification demonstrates the installed system does what it was designed to do. A site can hold a current calibration certificate for every instrument and still have no qualified operator for your process.
|
Artifact |
What it must contain |
Evidence it is complete |
Failure mode when missing |
|---|---|---|---|
|
Transfer package |
Synthetic route, conditions, reagents and critical parameters; HPLC and MS release methods with reference standards; íonachta, impurity, identity and content specifications; raw-material sources, prior batch records and known risks |
Signed transfer protocol with the four blocks above, plus a documented gap and risk list |
Scale-up deviations traced back to undocumented parameters, Shop with no baseline to investigate against |
|
Analytical method transfer record |
Method text, reference standards, system suitability criteria, acceptance criteria, comparative results at both sites |
Side-by-side results meeting pre-defined acceptance criteria, signed by both quality units |
Release testing that passes locally but does not reproduce the originating site’s result |
|
Operator qualification file |
Role-specific training records, verified understanding, equipment-specific and documentation-practice training, retraining triggers |
Qualification dated before the operator executes the protocol, with competency assessment on file |
Batch records signed by staff who were never qualified on that train or that documentation system |
|
IQ/OQ/PQ protocol set |
Design Qualification precedent; measurable acceptance criteria; IQ Protocol, IQ Checklist and IQ Report; OQ and PQ scope |
Completed reports with acceptance criteria met, plus the requalification trigger list Maidir |
Equipment in production with no documented basis for believing it performs as designed |
|
Batch record |
Contemporaneous entries, critical parameter values, deviations, CAPA references, review signatures |
Complete, attributable, legible, contemporaneous record released through QA |
A record reconstructed after the fact, which is a data-integrity finding rather than a documentation gap |
Use the table as a request list. Ask for each artifact by name, and ask which one the site cannot produce. The answer tells you more about peptide technology transfer readiness than any capability statement, and it is the same question you should be able to answer about your own site before you sign with anyone.
Documentation Discipline Is a Production Capability, Not a Record-Keeping Task

Contemporaneous documentation is what makes a batch defensible and a process reproducible, and it is a capability that has to be staffed, not a filing task that can be absorbed into someone’s spare hours.
The record set is specific. Batch records are completed as synthesis, workup, íonú, sampling and in-process testing happen, capturing yields and every handoff between operators. Logbooks cover equipment, rooms, balances, columns, freezers and utilities. Cleaning records show the equipment, method, date and time, operator, verification or release status, and line-clearance checks, because shared equipment creates carryover risk that only the cleaning record can rule out. Deviations are written up promptly with the actual batch impact and the containment taken, never resolved silently. CAPA ties a root cause to an effectiveness check. Change control covers suppliers, reagents, synthesis conditions, purification parameters, analytical methods, cleaning, software and acceptance criteria, which is what stops a process from drifting one undocumented adjustment at a time.
The standard behind this is the MHRA’s data-integrity guidance, which sets out the ALCOA principles: records must be attributable, legible, contemporaneous, original and accurate, with ALCOA+ adding complete, consistent, enduring and available (MHRA, retrieved 2026-06-11). ICH Q10 places that documentation inside a managed pharmaceutical quality system rather than alongside it (ICH, retrieved 2026-06-11).
One disclosure: the USP infographic and the EMA synthetic-peptides guideline could not be rendered on this platform, so the ALCOA and Q10 mapping above is presented as sound regulatory convention rather than as a directly quoted primary source.
The Counterargument: We Already Have GMP-Trained Staff and a Validated QMS
A site that already holds GMP-trained staff and a validated QMS starts far ahead of one that does not. That training and that quality system are genuine, transferable assets, and nothing in this argument asks a reader to discard them.
The gap is narrower and more specific. 21 CFR 211.25(a) requires training that enables each person to perform their assigned function, and that function is defined by the process, not by the QMS. A validated quality system governs how work is documented and released; it does not tell an operator where the fraction-collection window sits or how the column load is configured for a given peptide train. Those parameters arrive with the transfer package, and a complete one is what makes peptide technology transfer auditable rather than assumed. Táirgeadh Peptide
The adjacent objection is fair: domestic peptide workforce shortages are real, and the existing US and European peptide workforce is already fully employed. That shortage slows reshoring, and it also confirms where the constraint sits.
How to Apply This: Evaluating a Domestic Partner or Your Own Site
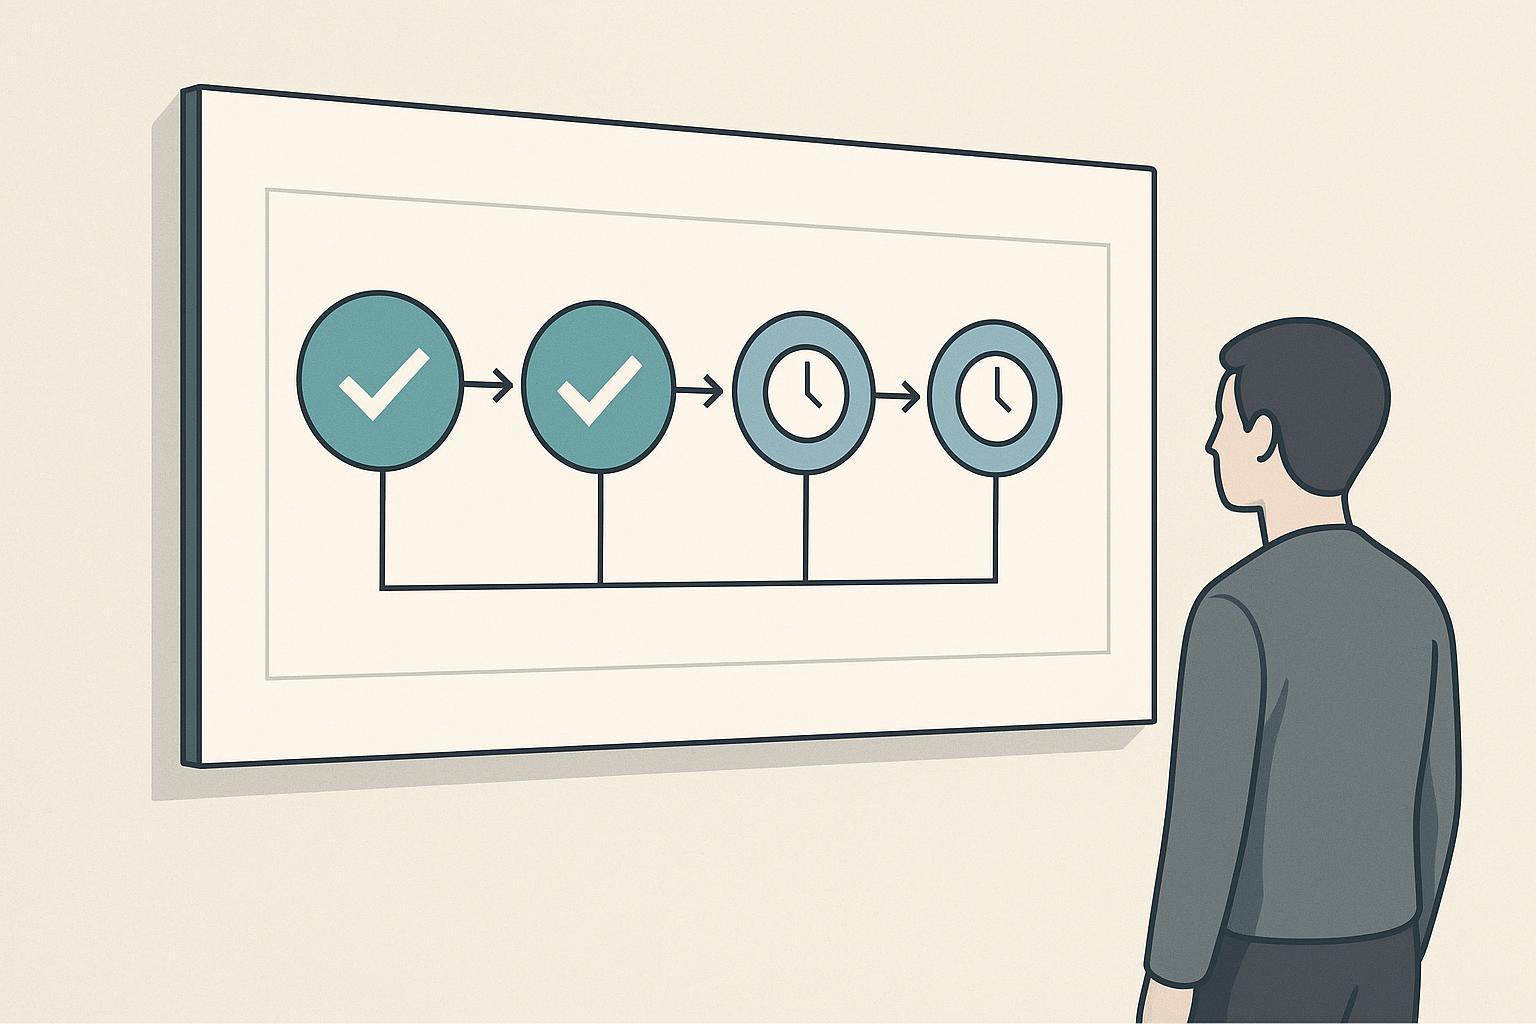
Start by auditing the transfer package, not the facility. A building can be inspected in a day; a transfer package that is missing its analytical methods will stall a program for months, and that is the failure mode worth screening for first.
Work through five steps in this order. The first two are quick wins measured in days to weeks; the last is a longer-term commitment.
-
Request the transfer package and check it against the artifact list. Days. Quick win. Ask for the process description, analytical methods, specifications, batch records and deviation history as a single indexed set. A package that arrives as scattered attachments is already telling you something about the documentation system behind it.
-
Verify analytical method transfer is sequenced first and gated before any batch. Weeks. Quick win. Method transfer and a demonstration batch typically run over a matter of weeks to a few months (Global Biotech Laboratories, 2026), and the method work has to close before the demonstration batch means anything.
-
Review operator qualification records for process-train-specific evidence and effectiveness checks. Weeks. A training record that shows attendance is not a qualification record. Under 21 CFR 211.25(a), training must enable the assigned function, which for a peptide line means the specific train, the specific equipment and the specific in-process controls that operator will run.
-
Walk the documentation system against ALCOA field by field. Weeks. Pick three executed batch records and trace attributable, legible, contemporaneous, original and accurate through each one. You are testing whether the system produces records that survive scrutiny, not whether a binder exists.
-
Confirm IQ/OQ/PQ scope, acceptance criteria and requalification triggers. Months. Longer-term. Equipment qualification should define measurable acceptance criteria and the conditions that force requalification, not just a completed protocol (The FDA Group, undated).
Key Takeaway: Audit in this order, transfer package completeness (days), method transfer gated before the first batch (weeks), process-train-specific operator qualification with effectiveness checks (weeks), ALCOA field-by-field documentation review (weeks), then IQ/OQ/PQ scope, acceptance criteria and requalification triggers (months). The first four are cheap and reveal most of what you need; the fifth is where the real time goes.
A worked example of what the auditable layer looks like: lot-specific traceability records that tie each batch to its raw material lots, and an in-house quality management system managed under QA rather than distributed across departments, give a partner something concrete to hand over during a transfer or audit discussion. MOL Changes operates that layer as part of its peptide synthesis and manufacturing workflow, and the records are the deliverable, not the relationship.
Track four things as you go: transfer-package completeness against the artifact list, method-transfer closure before the first batch, deviation and CAPA closure rates, and qualification currency across the operators assigned to your train. Expect weeks to months for the transfer mechanics and longer for qualification depth. The mechanics are the part you can compress with preparation; the depth is not.
Next step: If you are evaluating a domestic partner, request the transfer package and the qualification records before you schedule a site visit. Talk to a technical expert about what a complete package should contain for your specific peptide.
Disclosure: this article discusses peptide manufacturing process and quality practice, not regulatory advice. MOL Changes is a peptide synthesis and manufacturing provider; readers should evaluate any partner against their own quality and regulatory requirements.
Caveats: Where This Argument Is Weakest
The workforce-shortage evidence behind this argument is directional, not statistical. No verifiable 2026 shortage figure exists in the sources retrieved for this piece, and the strongest workforce quotations trace to a single vendor-adjacent publisher, Peptidestaff, which has a commercial interest in the conclusion. Treat the shortage as a well-supported pattern rather than a measured quantity.
The same caution applies to two numbers used above. Tá an 18 chuig 36 month conversion window and the 35 chuig 65 percent domestic cost premium are both single-upstream publisher estimates, not audited figures, and the premium moves with compound, scale and service scope. They are useful for planning ranges, not for a business case on their own.
Context matters in the other direction too. A site with deep peptide-specific experience, or one transferring a well-characterized mature process, may find the people layer largely solved already. This is a process and quality discussion, not regulatory or legal advice.
Frequently Asked Questions
But doesn’t the conventional approach work when the receiving site already runs the same platform?
It works better than a cross-platform transfer, but it does not remove the work. Global Biotech Laboratories describes the acceptance goal in any peptide technology transfer as “same molecule, same spec,” and that goal is met through a defined sequence of documentation, method verification and qualification steps rather than by shared equipment alone. Two sites can run identical synthesisers and still diverge on solvent lots, column history, gradient timing and operator technique. Same platform shortens the transfer; it does not close it.
What if we have already invested in a facility and now discover the people gap?
You are not alone, and the constraint is structural rather than personal. Peptidestaff notes that the existing workforce is already fully employed, which means the experienced operators you need are mostly working somewhere else and must be recruited or developed rather than hired off the market. The practical response is to treat recruitment and training as a project with its own schedule, budget and owner, running in parallel with equipment qualification rather than after it. Sites that sequence people last tend to hold a qualified facility idle while they wait.
How do you respond to the capacity projections that suggest the gap closes by 2029?
Those projections describe announced capacity, not available labour. Peptidestaff states that the 18% chuig 28% projection is based on announced investments and projected completion timelines, which is a statement about what companies have said they will build and when they expect to finish. Announced timelines slip, and a completed building does not staff itself. Figures of this type vary by source and by the assumptions behind them, so treat any single projection as a planning input rather than a settled forecast.
How much of this applies to analytical transfer versus process transfer?
More than most teams expect. Global Biotech Laboratories describes analytical method transfer as sequenced first, gating every downstream batch, which makes it the earlier and often the harder constraint. Process transfer gets the attention because it involves the large equipment, but if the receiving laboratory cannot reproduce the releasing methods, no batch can be released regardless of how well the synthesiser performs. Plan analytical transfer first and resource it accordingly.
Conclusion: The Industry Shift Reshoring Actually Requires
Capital builds peptide capacity; people and process convert it into reliable supply. That is the whole argument, and it is the reason reshoring peptide manufacturing will be decided in training rooms and transfer meetings rather than at the ribbon-cutting.
The shift this requires is structural, not rhetorical. Workforce development, transfer discipline and documentation capability have to be funded and staffed as first-class workstreams alongside facility capital, with their own budgets, owners and timelines. Treating them as downstream implementation details is what turns a commissioned plant into a plant that cannot release a lot.
The forward-looking version is straightforward. Domestic peptide supply becomes dependable when a qualified operator, a complete transfer package and a contemporaneous batch record are the ordinary case rather than the exception, and when capacity is operationalized only as fast as qualified people are hired, onboarded and trained.
If you are evaluating a domestic partner or your own site, start with the transfer package and the qualification evidence, then ask who signs the batch record. That conversation is worth having before the equipment arrives.
Disclosure: MOL Changes has a commercial interest in peptide quality standards and manufacturing services. This article is a process and quality discussion, not regulatory advice.





