Quick Answer
Oral peptide development hinges on five evidence criteria. See how oral candidates compare with injectables on stability, permeability and dose consistency
How oral peptide development is judged: the criteria that decide the comparison
Nte ar péptido oral ar juzga jar ku̲t'a ya criterios, ne xkagentho ku̲t'a da jäts'i kadu̲ 'nar sección 'mefa ár njäts'i Tange'u nuna ar comparación: nzäm'bu, permeabilidad, consistencia ar dosis, control ar degradación ne ar impureza, ne evidencia comparabilidad. yoho ya opciones nuwa ya paquetes evidencia, hingi proveedores. 'na ar ar candidato oral; ar ma'na ar control inyectable nä'ä tendría da desplazar.
punto partida ge ar tasa base. ar revisión PK-límites gi ungu̲mfädi da biodisponibilidad oral pa péptidos destinados pa nt'ot'e sistémica xi típicamente 1% 'nehe jár nkohi optimizadas, kontra ar aproximadamente 10-25% pa ar entrega insulina pulmonar. Ar aritmética multiplicación dosis pa ar biodisponibilidad sub — 1% te̲ni Hmunts'i: a 0.4-1.0% 'me̲i absoluta ko sustancial inter-- ne variabilidad intra — tema empuja dosis orales nu'bu mañä ya factores ar 10 to 100.
Do ndo'yo invita 'nar ñoho nt'a̲ni, Nu'bu̲ ar literatura gi 'ñudi cuán frecuencia fallan ya programas. Hingi bí muestra confiablemente. Ar complejidad ar revisión ar advertencia sesgo yá publicación ar explícita: Fracasos ne programas discontinuados ge sistemáticamente subreportados, Ngut'ä programas fallidos hingi xi contar ar confianza ndezu̲ ar registro publicado.
Key Takeaway: Juzgar 'nar candidato oral dige nzäm'bu, permeabilidad, consistencia ar dosis, control ar degradación ne ar impureza, ne evidencia comparabilidad. Jar evidencia nu'bya, Ningún candidato oral da to tratado komongu intercambiable ko ár control inyectable.
Quick comparison: what each option has to demonstrate
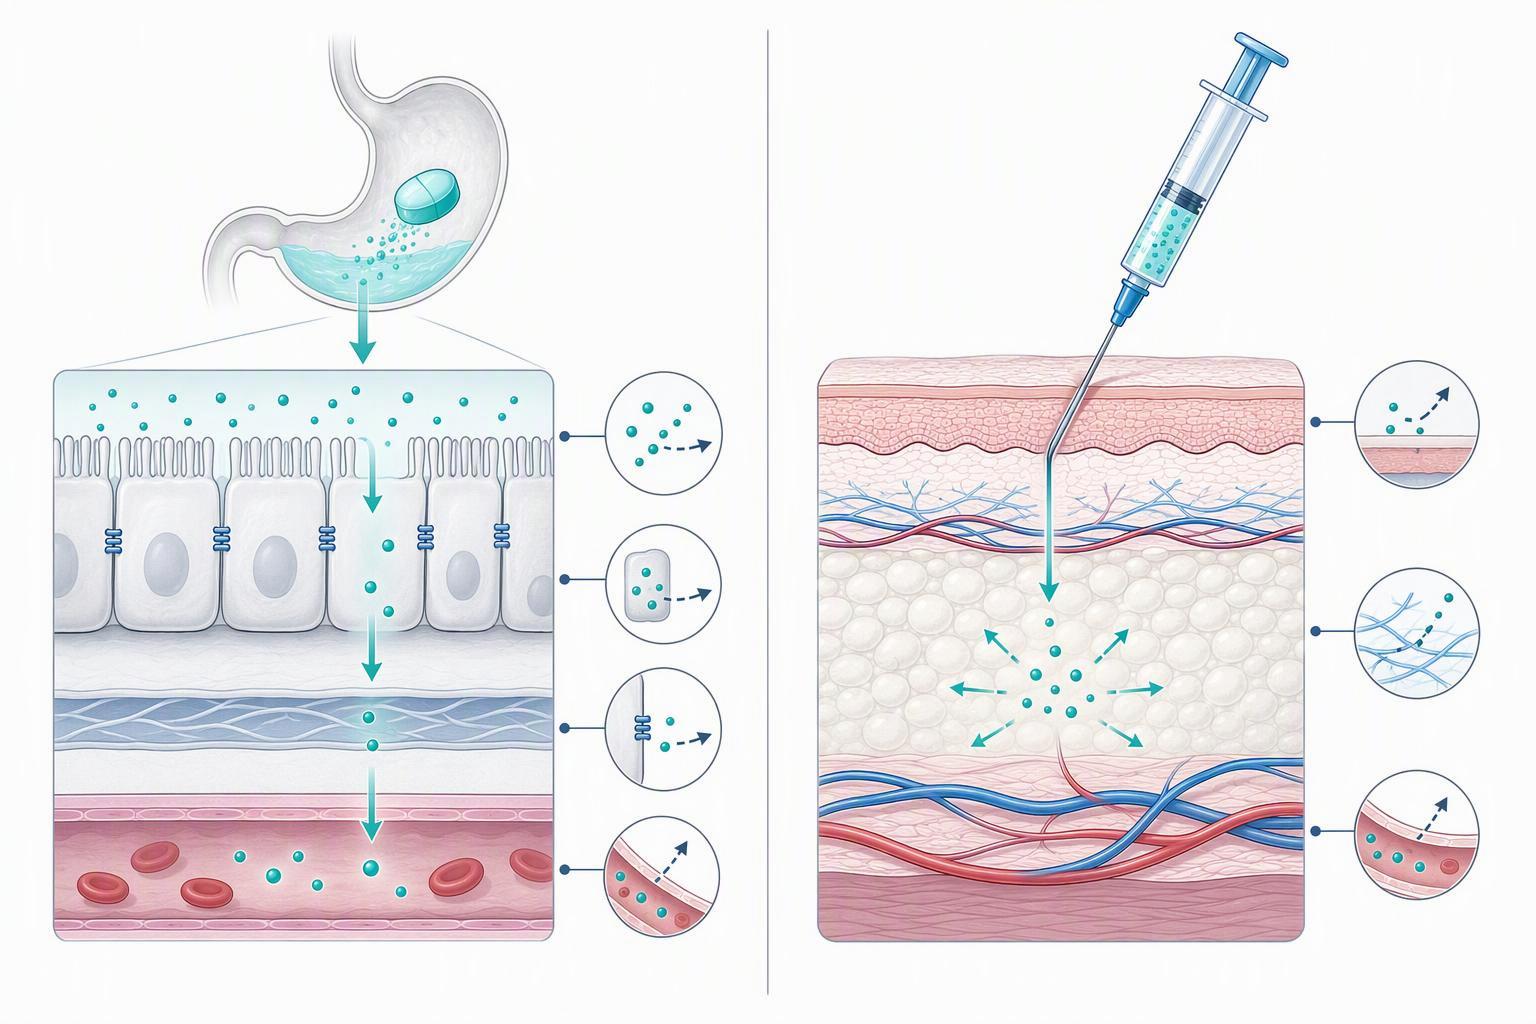
Ar comparación ar ar péptidos oral hä ar inyectable hingi ge 'nar nt'ot'e preferencia. ge 'nar nt'ot'e ar klase ar evidencia ya ruta to proporcionar, ne cuánto ar evidencia ya reguladores ne ya revisores aceptarán.
|
Requisito ar evidencia |
Candidato ar oral |
Control inyectable |
|---|---|---|
|
Ruta absorción |
a través de ar epitelio gástrico ne intestinal, ko 'nar potenciador ar permeación |
deposición directa subcutánea wa intramuscular |
|
Requisito ayuno |
obligatorio. ga̲tho ya formulaciones actuales ar peptídios orales requieren nkohi ayuno, ne dosificación ko nts'i resulta jar biodisponibilidad kasu̲ cero (fronteras jar entrega ar drogas, 2026) |
Ninguno |
|
multiplicación ar dosis |
típicamente 10 — 100 ya 'nandi ar dosis inyectable pa da tsoni ar exposición comparable |
Dosis referencia |
|
Variabilidad ar exposición |
Variación ar Cmax ne ar Tmax mäs nthegi xi hño; nts'i tsa̲ da reducir ar absorción aproximadamente 90% (Mycapssa prescripción ungumfädi, Sección 12.3, etiqueta actualizada 2025-07-24) |
apretado, control ya inyección ya inyección |
|
carga uniformidad contenido |
mextha: kadu̲ 'nar xe̲ni da tso̲ni cálculo valores nthä USP |
Inferior, Honto — ar xe̲ni ngetho ge |
|
Comparability evidence |
requiere exposición ar puente, Jar dätä hnini ayuno, ne datos ntsoni nts'i ja ar inyectable |
Perfil referencia establecida |
Fila multiplicación dosis ge nu'bu̲ da nthe̲hu̲ 'ra ho cambia ar comparación. Ja ar Nthuts'i ar etiqueta Mycapssa comparación 'nar dosis, 20 mg oral octreótide resultó jar exposición sistémica similar ma 0.1 mg subcutáneo octreotide, ko Cmax 33% zu'we ne Tmax 1.67 — 2,5 ora contra 0.5 ya ora.
kadu̲ 'nar fila 'be̲t'o bí bi pa̲ti ja 'nar criterio evaluación ja ya secciones nuya.
Stability: which option holds its potency through the shelf life?
Ar control inyectable ar mäs xi hño pa nzäm'bu da nu'bya xtä, ne gana 'nar mä estructural: ár péptido ho̲ntho pe̲ts'i da sobrevivir ar almacenamiento, mente da 'nar candidato oral da soportar ar almacenamiento ne gem'bu̲ ar tracto gastrointestinal.
esos gehya hñu modos falla distintos, not one. Chemical stability covers the peptide backbone and side chains. Proteolytic stability covers what gastric and intestinal enzymes do to the sequence after dosing. Excipient compatibility covers interactions between the peptide and everything formulated around it. A candidate can pass the first and fail the second, which is why a clean release profile says little about oral viability.
The probe set for the chemical question is established. ar ICH Q1A(R2) stress-testing matrix specifies temperature in 10 °C increments above accelerated conditions, humidity where appropriate, oxidation, photolysis, and hydrolysis across pH, and requires that the analytical methods separate the API from its degradants. Oxidation, �, hydrolysis and aggregation are the pathways that matrix is designed to expose.
The nuance matters: an injectable is not automatically stable. It carries cold-chain limits and its own aggregation risk. But its stability question stays a storage question. The oral candidate’s does not. ar calcitonin failure analysis shows how that gap closes a programme: insufficient gastric absorption, plasma concentrations at the limit of detection, and fibrilization-driven potency loss.
Permeability: which option gets the peptide across the barrier intact?
The injectable control wins this criterion outright, because it never has to cross the intestinal barrier at all. Permeability is the single largest source of the oral candidate’s dose penalty: class-wide oral bioavailability for peptides sits below 1% in most cases, as documented in the PK-boundaries review, which is why oral peptide formulation strategies revolve around permeation enhancers rather than around the peptide itself.
How those enhancers work is now better characterised. A 2025 study in Comunicaciones jar 'mui traced SNAC’s two-stage mechanism: it associates with the peptide in the aqueous layer and monomerizes it as a surfactant, then neutralizes and inserts into the lipid bilayer, forming dynamic SNAC-filled membrane defects through which the peptide sinks, in the authors’ phrasing, “analogous to quicksand,” with membrane integrity maintained afterwards. The route is transcellular, not paracellular.
The effect sizes remain modest and unstable. The tabulated enhancer effect sizes show C10 with LMWH at 3.9–7.6% relative, desmopressin at 2.4% relative to subcutaneous against roughly 0.2% for the marketed tablet, ISIS 104838 at 9.5% relative with an intra-subject range of 2–28%, and insulin tregopil at 1.5–2.0%. The same review notes massive intra-subject variability across all studies, so single-enhancer fixes for peptide stability and permeability are not supported by the clinical record.
Dose consistency: which option delivers a predictable exposure?
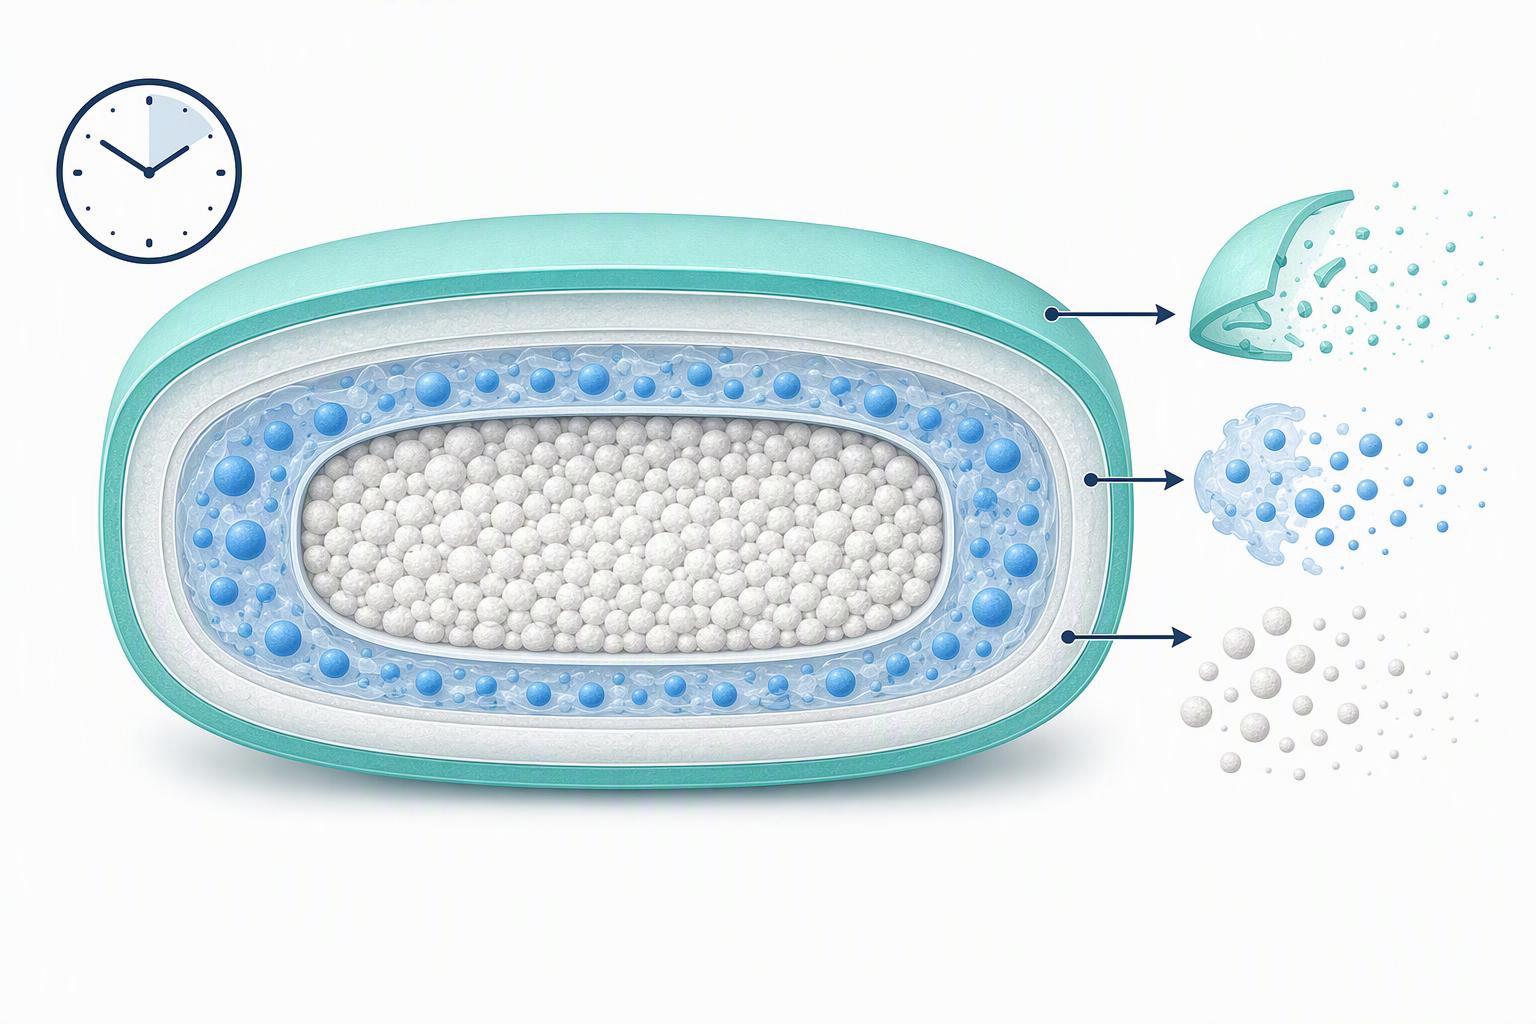
The injectable control wins on dose consistency, and the gap is structural rather than a matter of better manufacturing. A tablet can pass compendial content-uniformity testing and still deliver a variable absorbed fraction, because two independent sources of variance sit between the label claim and the systemic exposure.
The arithmetic behind that claim is the USP acceptance-value calculation, which sets AV = |M − X̄| + ks, with k = 2.4 for n = 10 ne 2.0 for n = 30, T = 100.0% by default, M = X̄ when X̄ falls between 98.5% ne 101.5%, AV ≤ L1 = 15.0, and no unit outside L2 = 25.0% deviation from M (USP General Chapter <905>). Passing that test constrains how evenly peptide is distributed across tablets. It says nothing about how much of each dose crosses the gut wall.
Services The population PK analysis of oral semaglutide puts the absorbed fraction at 0.795% absolute bioavailability (95% CI 0.736–0.864), with mean estimated F of 0.76% in healthy subjects and 0.69% in T2D, plateauing near 1.4% at 120 minutes post-dose fasting (Clinical Pharmacokinetics of Oral Semaglutide, 2021-05-10). At those fractions, the dose-multiplication arithmetic runs to roughly 100 times the parenteral dose for matched systemic exposure, so a small relative swing in absorbed fraction becomes a large absolute swing in exposure.
Formulation choices shift that fraction but do not remove the variability. In the oral semaglutide experience review, 300 mg SNAC was the optimal enhancer load: exposure was higher at 300 mg than at 150 i 600 mg, ne 300 mg is believed to avoid the precipitation seen at higher loads (The Oral Semaglutide Experience, 2023-08-22). The relationship is non-monotonic, which is why dose consistency for oral peptides has to be demonstrated across the enhancer range rather than at a single point.
Degradation and impurity control: which option is easier to characterise?
The oral candidate wins this criterion, and it wins for a structural reason rather than a chemical one: a tablet or capsule is a more tractable analytical object than a sterile injectable, because the sample is homogeneous, stable at bench conditions, and can be sampled unit by unit.
The stability-indicating set that supports the comparison is the same for both routes, but the oral route makes it easier to execute: identity by MS with sequencing or peptide mapping; purity and related substances by RP-HPLC or UPLC; impurity and degradant profiling by LC-MS; assay stated on an explicit gross-versus-net peptide content basis; unit-by-unit content uniformity; dissolution for release performance and formulation comparability; and formal long-term and accelerated stability with forced degradation. The forced-degradation probe set is defined by the ICH Q1A(R2) stress-testing matrix, which is what makes a degradant claim defensible rather than incidental.
Síntesis peptídica The injectable control is not the harder characterisation problem in every respect. Its impurity burden is dominated by aggregation, particulates, and sterility or endotoxin considerations, and endotoxin limits are arithmetic, not judgement: the FDA endotoxin limit arithmetic sets the threshold from K/M, 5.0 EU/kg for the intravenous route, ko a 0.5 EU/mL worked example. That is a defined number to hit.
A, r. In the calcitonin failure analysis, r, u, t, a, and fibrilization-driven potency loss. Purity that passes an HPLC threshold is not the same as purity that survives a discriminating biological assay, o.
Our finding: the oral candidate is easier to characterise in the dosage-form sense, and harder in the degradant sense. Both claims have to be made with the same analytical set, or the comparison is not a comparison.
Comparability evidence: what it takes to claim an oral candidate matches its injectable control
The injectable control wins this category by default. The comparability claim belongs s to the oral candidate, and the current evidence base does not discharge it.
The clearest worked example is the Mycapssa label’s single-dose comparison. In it, 20 mg oral octreotide produced systemic exposure (AUC) similar to 0.1 mg subcutaneous octreotide acetate, but peak plasma concentration (Cmax) was 33% lower by the oral route, and time to peak (tmax) arrived at 1.67 to 2.5 hours orally against 0.5 hours subcutaneously. Exposure was dose-proportional across 3 to 40 mg.
r, a. l, and that is a per-drug question, not a route-level one.
The regulatory framing sets the burden. Under FDA’s ANDA versus 505(b)(2) decision framework, an ANDA requires sameness to the reference listed drug in active ingredient, dosage form, route, strength, conditions of use and labeling, with only justified permitted differences. A 505(b)(2) applicant may rely in part on prior findings but must supply data supporting each difference, typically bioavailability or bridging, food-effect, and clinical or nonclinical data as needed.
Food effect is where that burden bites hardest. The Mycapssa label’s food-effect data record approximately 90% reduction in rate and extent of absorption with food, which is why dosing is tied to a fasting schedule rather than left to the patient.
Where the oral route wins, and where the injectable control still wins
The oral route wins where the barrier is not the problem. For gastrointestinal targets, the peptide acts where it already is, so the absorbed fraction stops being the deciding metric. Crohn’s disease, ulcerative colitis and gut-localised bacterial infections sit in that group, and the chemically modified classes built for it, double-bridged and cyclic peptides, hold their shape against enzymatic degradation long enough to matter. Non-invasive administration and patient-friendly use follow from the same logic.
A, r, or where the target is systemic and the absorbed fraction stays below 1%. o, p: c 1% i, � 0.4 to 1.0% �, n. Calcitonin is the cautionary case, i, n.
Key Takeaway: y. e 1%. c, the honest answer is a different route or a different modality, not a forced oral program.
The quality and analytical workflow that makes either comparison fair
A comparability claim is only as good as the analytical package behind it. The same stability-indicating set that characterises an oral candidate is what makes an injectable control a valid control: without a shared stress matrix, the two datasets describe different molecules under different conditions and no comparison holds. The ICH Q1A(R2) stress-testing matrix sets that shared baseline for forced degradation, and the FDA endotoxin limit arithmetic and the USP acceptance-value calculation extend it to safety and dose uniformity, so a reviewer can trace each number to a method rather than a summary.
Our finding: MOL Changes is an integrated organic-chemistry and biology R&D organization producing custom and modified peptides under Class 100 cleanroom conditions with HPLC, MS ne pruebas esterilidad. N, u, n.
nt'a̲ni frecuentes
Is an oral peptide interchangeable with its injectable control?
u. �, � 33% lower and arrived Synthetic Peptides at 1.67 to 2.5 p 0.5 ya ora. a: q, u.
¿Ar tsa̲ da comparar 'nar candidato oral ar justos nu'bu̲ ár biodisponibilidad xí abajo 1%?
Yes, e. A 0.4 to 1.0% r, t 10 to 100 r. e, v. About
Yogo'ä pe̲ts'i da zi ar jar ayuno?
i, s. i, � 90% �.
Temu̲ ya vías ar degradación importan mäs pa 'nar péptido oral?
Oxidation, �, n, e(R2) P. 'nar candidato oral te̲ni 'nar vía, ne ár control inyectable ni 'nar pa alcanza nä'ä: proteólisis gastrointestinal, ho ya enzimas digestivas descomponen ar péptido Ante da zo̲ni ar sitio absorción.
Ar nte ar péptido oral Tobe vale dá dí ntsa̲ perseguir?
pa moléculas específicas bajo nkohi dosificación específicas, ar registro aprobado hmä hä: semaglutida oral alcanzado 0.795% biodisponibilidad absoluta jar análisis PK jar nsa̲di ar semaglutida oral. Ar contrapeso ar real. análisis falla calcitonina documenta 'nar programa hingi sobrevivió, and the complexity review Publication — bias caveat ir bo̲ni ke ar leyt'i sobre-mfädi éxitos, nä'ä ar tasa base verdadera hingi ar conocible ar 'be̲fi publicada.
Njäts'i nu'bu
Ya veredictos ar criterios ya consistentes a través de ar comparación. Control inyectable gana jar consistencia ar dosis ne ar evidencia ar comparabilidad, ngetho ár exposición ar mide ne ár estándar referencia ar definido. Ar candidato oral gana nu'bu̲ ar objetivo ar ja wa ar ventana terapéutica ar nt'ot'e nthegi xi hño, ne ar mäs hei ar caracterizar nu'bu̲ ya conocidos ne analizados ya productos ar degradación. nzäm'bu ne permeabilidad siguen komongu ya yoho criterios ho ar ruta oral lleva ar carga ar evidencia mäs pesada.
Nä'ä xta ár nt'ent'i nja'bu̲. Da 'ñets'i oral nu'bu̲ ar objetivo ar ja wa ar ventana ar nt'ot'e ho 'bui ndunthe ne paquete evidencias xi completo. Da 'ñets'i ar control inyectable nu'bu̲ ar ventana xí estrecha, eficacia ar impulsada ar pico, wa ar fracción absorbida xi inferior 1%, ar techo nxo̲ge nsa̲di descrito ja ar revisión PK-fronteras. Ho ni 'na encaja, cambio ruta wa modalidad en lugar de forzar ar comparación. Read the Mycapssa label’s single-dose comparison as the benchmark for what matched exposure with a 33% lower Cmax and later tmax actually requires, and treat the complexity review’s publication-bias caveat as a warning against reading the literature as a clean scoreboard. Peptide Production
Commercial interest: MOL Changes supplies peptide synthesis and analytical services, so it has a commercial interest in peptide quality standards. This article is technical material for development teams, hingi asesoramiento médico.
If you are weighing an oral candidate, start with a technical feasibility assessment and request the documentation package: analytical data and sterility documentation for the peptide work you are scoping.