What Oral Peptide Delivery Changes in the Design Brief
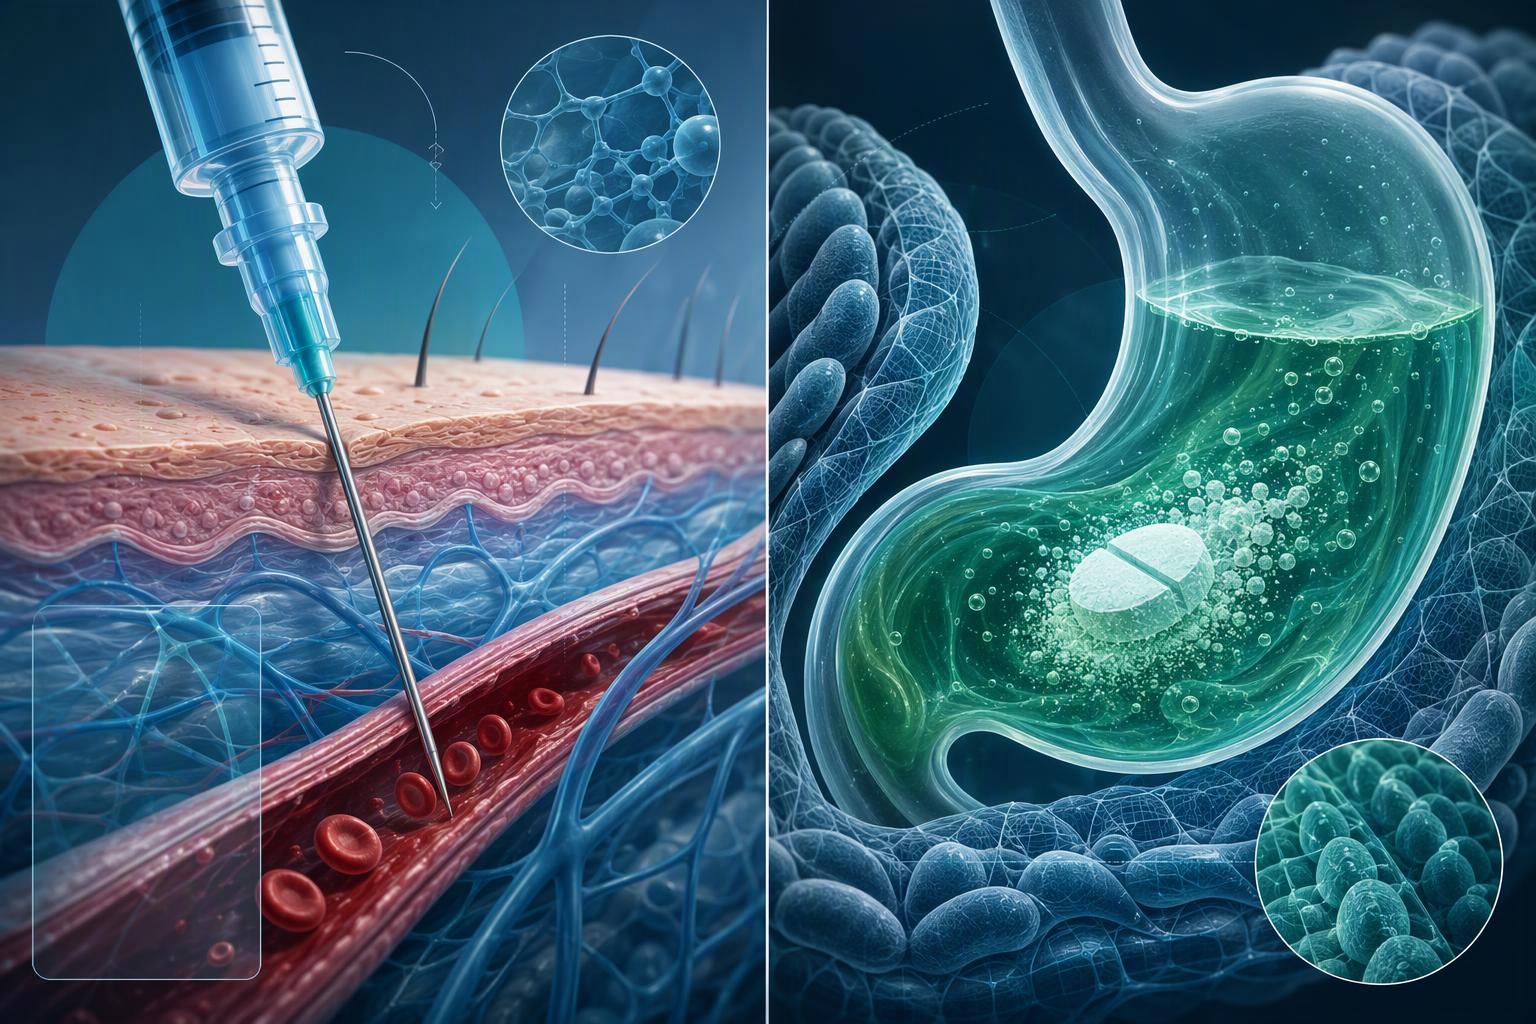
Kev xa peptide los ntawm qhov ncauj hloov lub hom phiaj tsim nws tus kheej. Hloov chaw txhim kho zog ua ntej thiab mam li tsim tom qab, cov txheej txheem thiab txoj kev xa khoom yuav tsum tau tsim ua ke txij thaum pib, vim tias molecule tam sim no yuav tsum ciaj sia dhau hauv plab ua ntej nws mus txog nws tus txais. Frontiers' review ntawm kev txwv pharmacokinetic ntawm kev muab peptide ncaj qha, luam tawm rau 20 Lub Peb Hlis 2026, frames the requirement as four survival conditions the peptide must satisfy at once: it must withstand gastric acid and proteases, resist aggregation, retain potency after modification, and carry a half-life long enough to compensate for a sub-1% absorbed dose.
That is a different brief from an injectable. An injected peptide bypasses the gastrointestinal tract entirely, so potency and half-life are the whole problem. An oral candidate carries those same requirements plus a delivery gauntlet, and the four conditions compete with each other: the modifications that improve protease resistance often work against permeability, and the ones that improve permeability often cost potency.

The Novo Nordisk and Hengrui Pharma licence for HRS-1596, announced on 29 Lub Cuaj Hli 2026, is worth reading in that light. Cov lus qhia yog $300 lab ua ntej, mus txog $2.6 txhiab lab hauv tag nrho tus nqi muaj peev xwm, ntxiv rau royalties ntawm kev muag khoom. Cov cuab yeej yog ib qho tshuaj glp-1/GIP dual receptor agonist ib zaug hauv ib lub lim tiam. Qhov uas tau tso cai tsis yog tsuas yog ib qho molecule xwb tab sis yog ib qho teeb meem xa khoom uas tau daws tau txaus los tsim ib qho Phase I programme.
⚠️ Warning: HRS-1596 raug qhia tias yog ib qho GLP-1/GIP dual receptor agonist ib zaug hauv ib lub lim tiam. tsab xov xwm no tham txog kev tsim peptide theem kev tshawb fawb thiab theem kev kho mob, tsis yog kev qhia kho mob. Thov tham nrog kws tshaj lij ua ntej txiav txim siab kho mob.
Why Oral Peptide Delivery Is Hard: The Three Barriers
Ib qho peptide hauv qhov ncauj yuav tsum ciaj sia dhau peb qhov kev thaiv sib txawv ua ntej nws mus txog hauv ntshav: kev puas tsuaj enzymatic hauv plab lumen, txheej epithelial cell, thiab txheej mucus npog phab ntsa plab. Txhua qhov tsis ua tiav vim ib qho laj thawj sib txawv, and each responds to a different design or formulation lever, which is why no single modification makes a peptide orally available.
The first barrier is chemical. Digestive proteases in the stomach and small intestine cleave the peptide backbone before absorption is even possible. An early screen of 17 peptides in simulated GI fluids found that enzymatic degradation, not pH, drove most of the loss, with cyclosporin, octreotide and desmopressin the notable exceptions (Molecular Pharmaceutics, 2015). That is a single-study result from one assay set, but it points designers toward backbone stabilization rather than enteric coating alone.
The second and third barriers are physical. A 2022 review of permeation-enhancer strategies describes permeability as a three-layer problem: luminal enzymes, the epithelial barrier with its paracellular, transcellular and carrier-mediated routes, and the mucus layer. The same review explains why permeation enhancers deliver only transient gains: they act locally, are payload-specific, and run into safety and tolerability limits at the doses needed.
That split matters for the intestinal permeability of peptides. Enzyme resistance, epithelial transport and mucus penetration each need their own fix, so oral programs are judged on the combination, not on any one modification.
Peptide Sequence Design for Oral Delivery
Oral delivery changes the design brief: sequence and modification choices must now serve stability and half-life, not potency alone. A peptide that loses its receptor affinity is useless, but one that is degraded before it reaches the intestinal wall never gets the chance to bind.
The standard chemical strategies for oral peptides are cyclization, D-amino acid substitution, other non-natural residues including N-methylation, lipidation or acylation, PEGylation and glycosylation. More rigid structures are generally less vulnerable to protease attack, as peer-reviewed reviews of cyclic peptides and oral delivery barriers describe. Cyclization buys conformational rigidity and some protease resistance; it does not by itself solve permeability.
Semaglutide shows how the two pillars combine. MOL Changes’ analysis of the oral GLP-1 development brief notes that the molecule pairs an Aib substitution at position 8, which blocks DPP-4 cleavage, with a Lys26 gamma-Glu-OEG2 spacer to a C18 di-acid for albumin binding: enzyme resistance plus half-life extension.
That second pillar carries a cost. Hydrophobic modifications that extend half-life, such as C18 di-acid acylation, lower aqueous solubility and raise aggregation tendency, narrowing the practical formulation window. Sequence decisions made at discovery therefore set the ceiling for everything downstream.
Stability Testing That Reflects the Gastrointestinal Tract
Oral peptide stability testing asks whether the peptide survives transit, not whether it survives storage. The developability assessment a peptide programme runs for an oral candidate is a GI-exposure programme: simulated gastric fluid and fasted-state simulated intestinal fluid, with and without enzymes, acid exposure, and precipitation risk as pH shifts from stomach to intestine (Bak et al., 2015). Injectable programmes target something else entirely, namely solution and shelf stability, u, oxidation, deamidation and container-closure compatibility.
The biorelevant stability toolkit at discovery stage is well defined. Simulated gastric fluid sits at roughly pH 1.2 with pepsin; fasted-state simulated intestinal fluid adds pancreatin; incubation runs at 37 °C with timed sampling; reversed-phase HPLC tracks intact peptide while LC-MS identifies fragments. Enzyme-free controls separate pH-driven hydrolysis from proteolysis.
Pro Tip: Run the enzyme-free control alongside every enzyme-containing sample. Without it, a loss of intact peptide cannot be attributed to proteolysis rather than acid hydrolysis, and the mechanism you need for redesign stays hidden.
That distinction carries the practical consequence. A programme that runs only shelf-life stability will not see the failure mode that eliminates oral candidates, because degradation in the gut happens on a timescale and through chemistry that storage studies never probe.
Intestinal Permeability and the Limits of Permeation Enhancement
Permeation enhancers raise the intestinal permeability of peptides at the margin, but they do not remove the ceiling. A 2026 review of oral peptide delivery complexity reports that most therapeutic peptides show oral bioavailability below 1%, describing this as the “low inherent oral bioavailability (<1%) observed for most compounds” (Oral peptide delivery complexity review, PMC, 2026-03-24). That figure is the baseline every oral program is working against.
Oral semaglutide shows what the best-characterised enhancer can achieve. Its absolute bioavailability is approximately 0.4% to 1% under strict fasting conditions, and near zero when taken with food, per a 2026 Frontiers review of oral peptide pharmacokinetic boundaries reporting the FDA clinical pharmacology review (Frontiers in Drug Delivery, 2026-03-20). The fasting requirement is not a labelling quirk; it is the mechanism showing through.
Y. u t a 2025 v, helps monomerise semaglutide in the water layer, u, a 1 kcal/mol versus a fixed protonation state. l, i, and tied to that payload.
c, a. s, a cyclic peptide from Chugai, S 21% to 47% N, A, C, reached approximately 6% p, a (b, 2026-03-24). The review presents MEDI7219 as a cross-compound comparison, not a head-to-head trial, so treat the multiple as directional.
Peptide 1 Why formulation alone rarely clears the low single-digit ceiling comes down to the excipient toolkit. Formulation efforts have relied on a small set of well-characterised excipients, “rarely yielding bioavailability’s beyond the low single-digit range in large animals and humans”; what enabled efficacy at low single-digit bioavailability in oral semaglutide, MK-0616 and icotrokinra was structural modification (b, 2026-03-24). Enhancers also carry a dose-limiting constraint: they act by disrupting the membrane, so safety and tolerability at the doses needed for absorption set a practical ceiling that varies by payload.
Formulation Screening and the Developability Gate
Formulation screening for an oral peptide is a staged elimination process, not an excipient search. The formulation screening funnel runs excipient compatibility and stability screening first, then function-based multi-excipient selection, enteric protection so release happens after the stomach, permeation-enhancer screening, and dose-loading feasibility, before any candidate reaches biorelevant release testing (PMC and Bak et al., 2015). Each stage exists to remove candidates cheaply, and constrained loading is a hard design limit: helper excipients compete with the peptide for space in the dosage form, so every added functional excipient takes room the dose needs.
Solid State Peptide Synthesis Potency and half-life are entry criteria for the oral route, not downstream properties. The potency gate for oral candidates is a low-nanomolar EC50, because low potency cannot achieve efficacy at a sub-1% absorbed dose (Frontiers, 2026). The half-life gate for once-daily oral dosing sets approximately 24 hours or more as the practical minimum when bioavailability sits below 1%; 12 to 24 hours stays viable only with twice-daily dosing or compensating potency and therapeutic window (Frontiers, 2026).
|
Technical area |
Pass condition |
Failure signal |
|---|---|---|
|
Sequence design |
Low-nanomolar EC50; modification strategy compatible with scale-up |
Potency requires a dose the dosage form cannot carry |
|
Peptide stability testing |
Intact peptide survives simulated gastric and intestinal conditions |
Rapid degradation before the absorptive surface |
|
Intestinal permeability of peptides |
Measurable flux with an enhancer strategy that tolerates chronic dosing |
Permeability gains that reverse at repeat exposure |
|
Formulation |
Enteric protection plus dose loading that fits the capsule |
Excipient load crowds out the peptide |
|
Analytical characterization |
Kev ntsuas cais peptide uas tseem nyob ntawm metabolites thiab degradants |
Kev kuaj tso tawm uas tsis tuaj yeem daws tau cov tshuaj uas tau nqus |
Qhov tshwm sim tiag tiag: Ib qho program uas tsis tuaj yeem tshem tawm potency thiab half-life gates thaum pom tsawg heev rov qab tau lawv Liberty Blue Peptide Synthesizer Tom qab, Yog li ob qho no yog ib feem ntawm kev xaiv tus neeg thov ua ke nrog kev kuaj peptide ruaj khov thiab permeability plan.
Analytical Characterization for Oral Programs
Cov kev pab cuam hauv qhov ncauj yuav tsum ntxiv biorelevant-medium degradant profiling rau kev kuaj tso tawm ib txwm. Ib pob tshuaj ntsuam tsim rau tshuaj txhaj yuav tsis piav qhia txog cov degradants uas qhov kev pab cuam qhov ncauj tiag tiag tsim.
Qhov ntawd txhais tau tias muaj peb ntxiv. First, Kev ruaj ntseg ntawm sequence thiab kev hloov kho: Kev lees paub lub hauv paus thiab cov residues uas tsis yog ntuj tsim nyob zoo. Thib ob, Kev txheeb xyuas degradation-product hauv cov khoom ua qauv gastric thiab intestinal media, not just in buffer. Third, counterion and salt-form characterization, since trifluoroacetate exchange affects both assay accuracy and tolerability. Endotoxin testing by LAL assay and a complete certificate of analysis belong in the same package, thiab ISO 13485 or ISO 9001 context tells you whether the supplier’s quality system can support it.
Methods must be validated against the validation characteristics Q2(R2) Qhia tawm, published by the FDA in March 2024. Read those as expectations rather than thresholds: the guideline gives signal-to-noise guidance of roughly 3:1 for detection limit and at least 10:1 for quantitation limit, not peptide-specific cutoffs.
Qhov tseem ceeb: A validated peptide analytical characterization package should cover specificity and selectivity, o, precision Peptide 2 including repeatability and intermediate precision, x, response and linearity, detection and quantitation limits, and robustness.
This is where a research-grade supplier stops being enough. A 95% purity floor is a conventional research-grade baseline, but it says nothing about which degradants are present or whether the method that measured it was validated for an oral matrix.
Discovery-Stage Synthesis Needs Versus Development and Scale-Up
Discovery and development optimise for different things. Discovery optimises for learning: many analogues, milligram to small research quantities, screening-grade purity acceptable, and turnaround valued over process optimisation. Development optimises for dependable manufacturing: fewer routes, locked and transferable processes, tight impurity control, lot-to-lot comparability, gram-to-kilogram supply, and full analytical and regulatory documentation. The change of optimisation target at scale-up, not the batch size alone, is what breaks programs, as the discovery-to-development framing in Bak et al.’s developability primer sets out (2015).
|
Requirement |
Discovery |
Development and scale-up |
|---|---|---|
|
Scale |
Milligram to small research quantities |
Gram to kilogram |
|
Purity target |
Screening grade acceptable |
Tight impurity control, lot-to-lot comparability |
|
Process status Cem Peptide Synthesis |
Many analogues, routes still open |
Fewer routes, locked and transferable |
|
Analytical package Peptide 2 |
Identity and rough purity |
Full characterisation and regulatory documentation |
Peptide scale-up failure modes concentrate in incomplete coupling and deprotection, aggregation and poor resin swelling or mass transfer, thermal gradients, and purification bottlenecks. Small inefficiencies compound across every amino-acid addition, so yield and purity loss from milligram to kilogram scale is real but not reported as a percentage in any primary source, yog li ntawd thiaj piav qhia ntawm no es tsis yog suav.
Qhov tseem ceeb: Xaiv koj tus khub synthesis raws li theem koj tab tom nkag mus, tsis yog theem koj nyob. Ib txoj kev uas tso cai rau kev huv huv zoo li kev tshuaj xyuas ntawm milligram scale yuav tsis nqa ib qho program mus rau gram-kilogram yam tsis muaj kev kaw txheej txheem thiab ntawv pov thawj tag nrho.
MOL Changes khiav kev tsim peptide tshwj xeeb los ntawm milligram mus rau kilogram scale, nrog sequences mus txog 200 amino acids thiab kev txhawb nqa rau 300-plus modifications, thiab purity los ntawm crude mus dhau 99 feem pua. Cov txheej txheem tswj xyuas zoo muaj xws li HPLC, LC-MS, endotoxin testing, thiab sterility testing hauv Class 100 cleanroom.
Common Misconceptions About Oral Peptide Delivery
plaub kev ntseeg ua rau feem ntau ntawm cov kev ua tsis tiav kim hauv cov peptide programming: tias permeation enhancer daws tau absorption, tias kev xa tawm ntawm qhov ncauj yog teeb meem ntawm kev tsim qauv tsis yog teeb meem molecule, tias ib qho peptide ruaj khov yog ib qho peptide ruaj khov rau hauv txee, thiab tias kev nce qib tsuas yog ib pawg loj dua.
Ob qho thawj no muaj kev sib raug zoo. Cov tshuaj txhawb nqa ua haujlwm ib ntus thiab hauv zos ntawm phab ntsa plab, yog li lawv nthuav qhov rais es tsis yog tshem tawm qhov thaiv. Dab tsi hloov qhov kev pom rau cov peptides hauv qhov ncauj yog kev hloov kho qauv, yog li ntawd kev tsim ib leeg tsis txaus kom dhau qhov qis tshaj plaws ntawm kev nqus tau uas cov kev pab cuam hauv qhov ncauj ntsib. Yog tias koj pab pawg tab tom tshuaj xyuas excipients ua ntej cov txheej txheem tau kho kom zoo rau hauv plab, kev tshuaj xyuas yog ua ntej sijhawm.
Kev nkag siab yuam kev thib peb ua rau ob qho kev ntsuas sib txawv. Kev tiv thaiv kev raug mob hauv plab thiab kev ruaj ntseg ntawm lub sijhawm khaws cia yog cov yam ntxwv sib txawv, thiab ib qho peptide uas nyob tau kaum ob lub hlis ntawm ib lub tais tseem yuav raug puas tsuaj ua ntej nws mus txog qhov chaw nqus tau.
Q, h. o, v.
⚠️ Warning: Oral bioavailability for peptides remains low and variable. t. h, i, b, or approval claim.
Cov Lus Nug Nquag Nug
What oral bioavailability does a peptide need to be worth developing?
p, l. a 24 u, b. K, e.
Why must oral semaglutide be taken on an empty stomach?
v. The fasting requirement for oral semaglutide reflects an absolute bioavailability of approximately 0.4-1% under strict fasting conditions, n 4 o, j, and a 30-minute fast after dosing, t, a. u.
Can permeation enhancers make any peptide orally available?
PM. Enhancers such as SNAC work by creating transient defects in the intestinal membrane that let the co-formulated peptide cross, y, o, g. An enhancer that carries one peptide across the epithelium will not necessarily carry another, and raising the dose runs into gastrointestinal tolerability limits. Permeation enhancement widens the window for a candidate that already has the right potency and half-life; it does not make an arbitrary peptide absorbable.
Kev kuaj ruaj khov li cas uas ib qho kev pab peptide noj yuav tsum tau uas ib qho kev pab cuam txhaj tsis xav tau?
An oral program needs stability data generated in gastrointestinal-relevant media, not just in buffer. Injectable programs characterise the peptide in formulation buffer and plasma; oral candidates additionally have to survive gastric acid, pepsin, and intestinal proteases, so peptide stability testing has to model those conditions rather than assume them. That means proteolytic stability assays in simulated gastric and intestinal fluid, and release methods that reflect the intestinal environment the capsule actually encounters.
Yuav tsum muaj kev huv ntawm theem tshawb nrhiav thiab theem kev loj hlob txawv li cas?
Discovery work tolerates crude to 95% purity, because the question being asked is whether the sequence behaves, not whether it can be filed. Development and scale-up work moves toward 99% purity with a documented analytical package, since the same material has to support toxicology, clinical supply, and regulatory review. A sequence that looks clean at research grade can reveal impurity and stability problems once the purity floor rises.
Novo thiab Hengrui deal qhia li cas tiag tiag?
It signals that large pharmaceutical companies are willing to pay for oral peptide delivery capability rather than build it. Hengrui’s announcement of the HRS-1596 licence disclosed a deal worth up to approximately $300 million for an oral GLP-1/GIP candidate, with Novo Nordisk taking the development forward. The signal for anyone running an oral program is the structure rather than the headline number: the licensor retained the discovery and early development work, and the partner bought the later-stage capability.
Xaus thiab Kauj Ruam Tom Ntej
Oral peptide delivery moves five decisions earlier and makes them interdependent: sequence design, stability testing, permeability strategy, formulation screening and analytical characterization. Change one and the others move with it, which is why the evaluation sequence matters more than any single modification. A candidate that survives fasted-state intestinal media but fails the developability gate is not a near-miss; it is a program that needed the permeability question answered before the synthesis scale changed.
That is also where the stage distinction earns its keep. Discovery work tolerates crude material and rapid iteration, while development and peptide scale-up demand documented purity, validated methods and batch-to-batch consistency. The handoff points between those stages, not the individual steps, are where programs lose time.
The HRS-1596 licence announced on 29 Lub Cuaj Hli 2026 is one signal in a broader shift: delivery capability, not receptor potency alone, is becoming the differentiator. HRS-1596 is disclosed as phase I-ready for once-weekly oral dosing, and no efficacy or approval claim follows from that disclosure. Oral bioavailability remains low and variable, and no single modification or excipient resolves permeability on its own.
If you are scoping an oral candidate, the useful next step is a capability conversation: talk to an expert about which stage your sequence sits at and what the data package needs to show.
Disclosure: MOL Changes provides custom peptide synthesis services. This article discusses research-stage and clinical-stage peptide development and is not medical advice; consult a qualified professional before making medical decisions.