Mitä suun kautta otettava peptidin annostelu muuttaa suunnitteluselosteessa
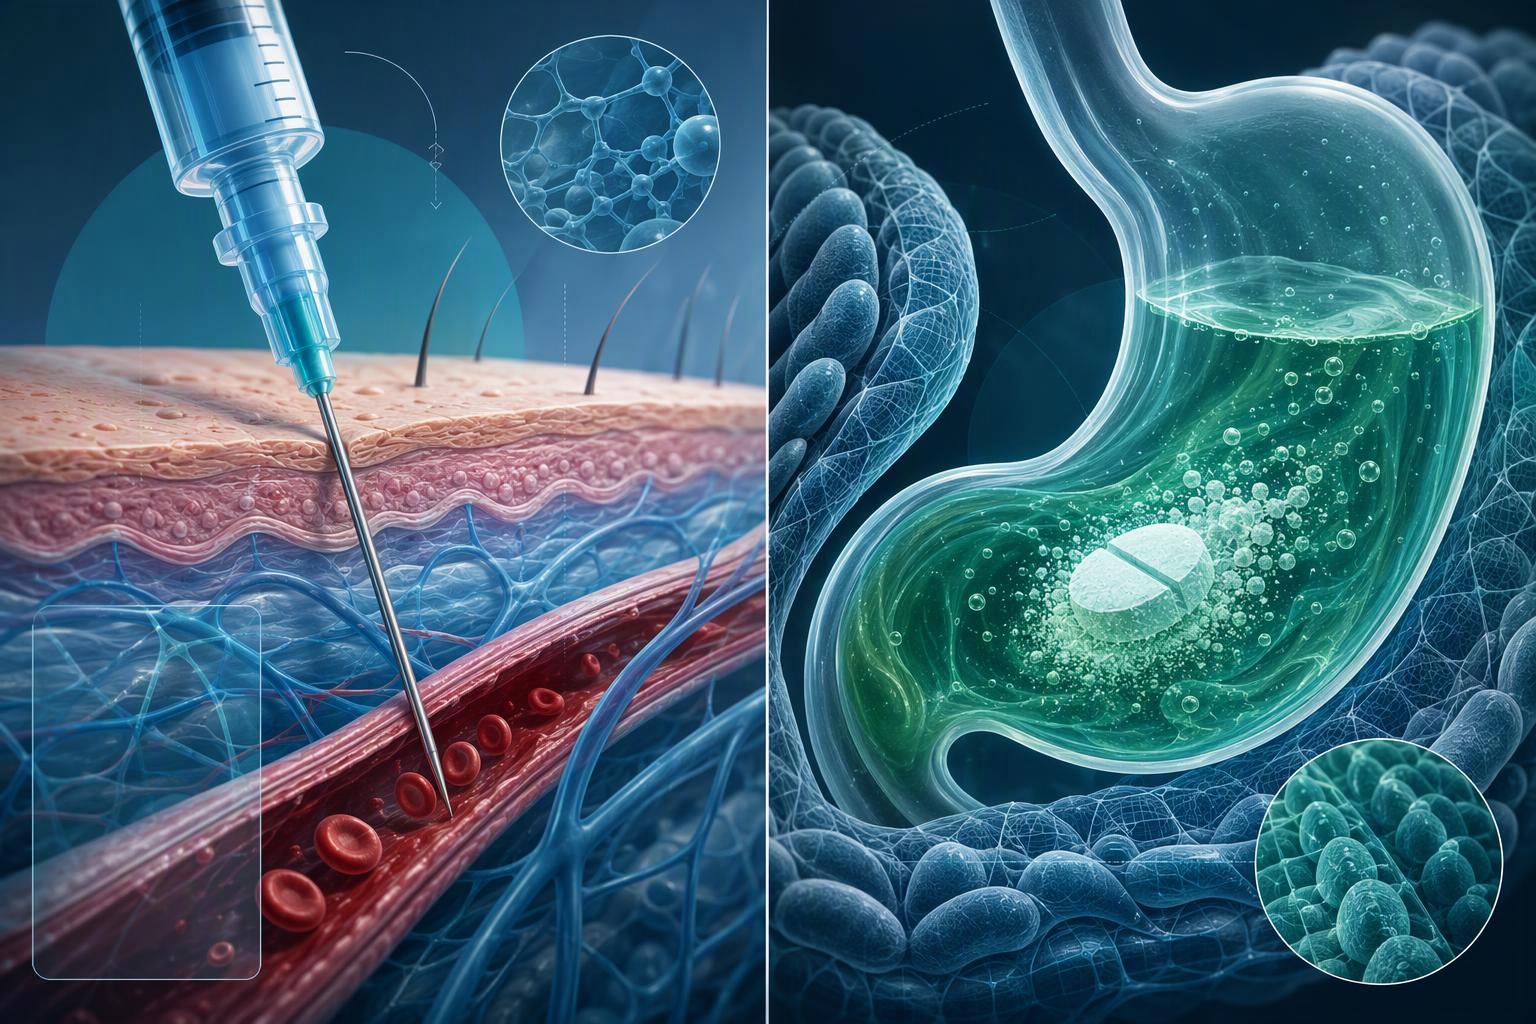
Suun kautta tapahtuva peptidin annostelu muuttaa itse suunnittelun tavoitetta. Sen sijaan, että optimoit tehokkuutta ensin ja muotoilet myöhemmin, järjestys ja toimitusstrategia on suunniteltava yhdessä alusta alkaen, koska molekyylin on nyt selviydyttävä suolesta ennen kuin se voi koskaan saavuttaa reseptorinsa. Frontiersin katsaus oraalisen peptidiannostuksen farmakokineettisiin rajoihin, julkaistu 20 maaliskuuta 2026, kehystää vaatimuksen neljänä selviytymisehtona, jotka peptidin on täytettävä kerralla: sen on kestettävä mahahappoa ja proteaaseja, vastustaa aggregaatiota, säilyttää teho muuntamisen jälkeen, ja niiden puoliintumisaika on riittävän pitkä kompensoimaan alle 1 %:n imeytyneen annoksen.
Se on erilainen kuin injektio. Injektoitu peptidi ohittaa maha-suolikanavan kokonaan, joten teho ja puoliintumisaika ovat koko ongelma. Suullisella hakijalla on samat vaatimukset sekä toimitushansi, ja neljä ehtoa kilpailevat keskenään: modifikaatiot, jotka parantavat proteaasiresistenssiä, toimivat usein läpäisevyyttä vastaan, ja ne, jotka parantavat läpäisevyyttä, maksavat usein tehoa.

Novo Nordiskin ja Hengrui Pharman lisenssi HRS-1596:lle, ilmoitettu 29 syyskuu 2026, kannattaa lukea siinä valossa. Ilmoitetut ehdot ovat $300 miljoonaa etukäteen, asti $2.6 miljardia potentiaalista kokonaisarvoa, plus rojaltit liikevaihdosta. Omaisuus on kerran viikossa oraalinen GLP-1/GIP-kaksoisreseptoriagonisti. Se, mitä lisensoidaan, ei ole vain molekyyli, vaan toimitusongelma, joka on ratkaistu tarpeeksi pitkälle oikeuttaakseen vaiheen I ohjelman.
⚠️ Varoitus: HRS-1596 esitetään kerran viikossa suun kautta otettavana GLP-1/GIP-kaksoisreseptoriagonistina. Tässä artikkelissa käsitellään tutkimusvaiheen ja kliinisen vaiheen peptidien kehitystä, ei lääkärin neuvoja. Neuvottele pätevän ammattilaisen kanssa ennen kuin teet mitään lääketieteellistä päätöstä.
Miksi peptidin antaminen suun kautta on vaikeaa: Kolme estettä
Suun kautta otettavan peptidin on selviydyttävä kolmesta erillisestä esteestä ennen kuin se pääsee verenkiertoon: entsymaattinen hajoaminen suoliston luumenissa, epiteelisolukerros, ja suolen seinämää peittävä limakerros. Jokainen epäonnistuu eri syystä, ja jokainen vastaa eri suunnittelu- tai formulointivivuille, tästä syystä mikään yksittäinen modifikaatio ei tee peptidistä suun kautta saatavaa.
Ensimmäinen este on kemiallinen. Ruoansulatusproteaasit mahassa ja ohutsuolessa katkaisevat peptidirungon ennen kuin imeytyminen on edes mahdollista. Varhainen näyttö 17 peptidit simuloiduissa GI-nesteissä havaitsivat, että entsymaattinen hajoaminen, ei pH, ajoi suurimman osan tappiosta, syklosporiinin kanssa, oktreotidi ja desmopressiini ovat merkittäviä poikkeuksia (Molecular Pharmaceutics, 2015). Tämä on yhden tutkimuksen tulos yhdestä määrityssarjasta, mutta se ohjaa suunnittelijoita pikemminkin selkärangan stabilointiin kuin yksinomaan enteropinnoitteeseen.
Toinen ja kolmas este ovat fyysisiä. A 2022 läpäisyä parantavien strategioiden tarkastelu kuvaa läpäisevyyttä kolmikerroksiseksi ongelmaksi: luminaaliset entsyymit, epiteelin este ja sen parasellulaarinen, transsellulaarisia ja kantajavälitteisiä reittejä, ja limakerros. Sama katsaus selittää, miksi läpäisevyyden tehostajat tuottavat vain ohimeneviä vahvistuksia: he toimivat paikallisesti, ovat hyötykuormakohtaisia, ja joutua turvallisuuden ja siedettävyyden rajoihin tarvittavilla annoksilla.
Tällä jakautumisella on merkitystä peptidien suoliston läpäisevyyden kannalta. Entsyymiresistenssi, epiteelin kuljetus ja liman tunkeutuminen tarvitsevat kukin oman korjauksensa, joten suulliset ohjelmat arvioidaan yhdistelmän perusteella, ei mihinkään muutokseen.
Peptidisekvenssisuunnittelu suun kautta tapahtuvaa annostelua varten
Suullinen toimitus muuttaa suunnitteluohjetta: sekvenssi- ja muunnosvalintojen on nyt palveltava vakautta ja puoliintumisaikaa, ei pelkästään tehoa. Peptidi, joka menettää reseptoriaffiniteettinsa, on hyödytön, mutta se, joka hajoaa ennen kuin se saavuttaa suolen seinämän, ei saa koskaan mahdollisuutta sitoutua.
Oraalisten peptidien standardikemialliset strategiat ovat syklisointi, D-aminohapposubstituutio, muut ei-luonnolliset jäännökset mukaan lukien N-metylaatio, lipidation or acylation, PEGylation and glycosylation. More rigid structures are generally less vulnerable to protease attack, kuten peer-reviewed reviews of cyclic peptides and oral delivery barriers describe. Cyclization buys conformational rigidity and some protease resistance; it does not by itself solve permeability.
Semaglutide shows how the two pillars combine. MOL Changes’ analysis of the oral GLP-1 development brief notes that the molecule pairs an Aib substitution at position 8, which blocks DPP-4 cleavage, with a Lys26 gamma-Glu-OEG2 spacer to a C18 di-acid for albumin binding: enzyme resistance plus half-life extension.
That second pillar carries a cost. Hydrophobic modifications that extend half-life, such as C18 di-acid acylation, lower aqueous solubility and raise aggregation tendency, narrowing the practical formulation window. Sequence decisions made at discovery therefore set the ceiling for everything downstream.
Vakaustesti, joka heijastaa maha-suolikanavaa
Oral peptide stability testing asks whether the peptide survives transit, not whether it survives storage. The developability assessment a peptide programme runs for an oral candidate is a GI-exposure programme: simulated gastric fluid and fasted-state simulated intestinal fluid, with and without enzymes, acid exposure, and precipitation risk as pH shifts from stomach to intestine (Bak et al., 2015). Injectable programmes target something else entirely, namely solution and shelf stability, yhdistäminen, hapettumista, deamidation and container-closure compatibility.
The biorelevant stability toolkit at discovery stage is well defined. Simulated gastric fluid sits at roughly pH 1.2 with pepsin; fasted-state simulated intestinal fluid adds pancreatin; incubation runs at 37 °C with timed sampling; reversed-phase HPLC tracks intact peptide while LC-MS identifies fragments. Enzyme-free controls separate pH-driven hydrolysis from proteolysis.
Vihjeille: Run the enzyme-free control alongside every enzyme-containing sample. Ilman sitä, a loss of intact peptide cannot be attributed to proteolysis rather than acid hydrolysis, and the mechanism you need for redesign stays hidden.
That distinction carries the practical consequence. A programme that runs only shelf-life stability will not see the failure mode that eliminates oral candidates, because degradation in the gut happens on a timescale and through chemistry that storage studies never probe.
Suolen läpäisevyys ja läpäisevyyden parantamisen rajat
Permeation enhancers raise the intestinal permeability of peptides at the margin, but they do not remove the ceiling. A 2026 review of oral peptide delivery complexity reports that most therapeutic peptides show oral bioavailability below 1%, describing this as the “low inherent oral bioavailability (<1%) observed for most compounds” (Oral peptide delivery complexity review, PMC, 2026-03-24). That figure is the baseline every oral program is working against.
Oral semaglutide shows what the best-characterised enhancer can achieve. Its absolute bioavailability is approximately 0.4% to 1% under strict fasting conditions, and near zero when taken with food, per a 2026 Frontiers review of oral peptide pharmacokinetic boundaries reporting the FDA clinical pharmacology review (Frontiers in Drug Delivery, 2026-03-20). The fasting requirement is not a labelling quirk; it is the mechanism showing through.
How SNAC actually helps semaglutide cross the membrane is more specific than a lipophilicity boost. Work published in Luontoviestintä in October 2025 found that SNAC forms permeation-enhancer-filled fluid membrane defects, helps monomerise semaglutide in the water layer, then neutralises to insert into the bilayer, lowering aqueous free energy by about 1 kcal/mol versus a fixed protonation state. The effect is transient, local, and tied to that payload.
Higher numbers exist, and they are outliers rather than a template. The Luna18 preclinical outlier, a cyclic peptide from Chugai, reaches 21% to 47% oral bioavailability in preclinical models, and the MEDI7219 dog study, an AstraZeneca enteric-coated tablet, reached approximately 6% in dogs, about a five-fold increase over semaglutide formulated with SNAC (PMC complexity review, 2026-03-24). The review presents MEDI7219 as a cross-compound comparison, not a head-to-head trial, so treat the multiple as directional.
Peptidi 1 Why formulation alone rarely clears the low single-digit ceiling comes down to the excipient toolkit. Formulation efforts have relied on a small set of well-characterised excipients, “rarely yielding bioavailability’s beyond the low single-digit range in large animals and humans”; what enabled efficacy at low single-digit bioavailability in oral semaglutide, MK-0616 and icotrokinra was structural modification (PMC complexity review, 2026-03-24). Enhancers also carry a dose-limiting constraint: they act by disrupting the membrane, so safety and tolerability at the doses needed for absorption set a practical ceiling that varies by payload.
Formulaatioseulonta ja kehitysportti
Formulation screening for an oral peptide is a staged elimination process, not an excipient search. The formulation screening funnel runs excipient compatibility and stability screening first, then function-based multi-excipient selection, enteric protection so release happens after the stomach, permeation-enhancer screening, and dose-loading feasibility, before any candidate reaches biorelevant release testing (PMC and Bak et al., 2015). Each stage exists to remove candidates cheaply, and constrained loading is a hard design limit: helper excipients compete with the peptide for space in the dosage form, so every added functional excipient takes room the dose needs.
Solid State Peptide Synthesis Potency and half-life are entry criteria for the oral route, not downstream properties. The potency gate for oral candidates is a low-nanomolar EC50, because low potency cannot achieve efficacy at a sub-1% absorbed dose (Frontiers, 2026). The half-life gate for once-daily oral dosing sets approximately 24 hours or more as the practical minimum when bioavailability sits below 1%; 12 to 24 hours stays viable only with twice-daily dosing or compensating potency and therapeutic window (Frontiers, 2026).
|
Technical area |
Pääsyn kunto |
Failure signal |
|---|---|---|
|
Sequence design |
Low-nanomolar EC50; modification strategy compatible with scale-up |
Potency requires a dose the dosage form cannot carry |
|
Peptide stability testing |
Intact peptide survives simulated gastric and intestinal conditions |
Rapid degradation before the absorptive surface |
|
Intestinal permeability of peptides |
Measurable flux with an enhancer strategy that tolerates chronic dosing |
Permeability gains that reverse at repeat exposure |
|
Formulation |
Enteric protection plus dose loading that fits the capsule |
Excipient load crowds out the peptide |
|
Analyyttinen karakterisointi |
Assay distinguishes intact peptide from metabolites and degradants |
Release testing that cannot resolve the absorbed species |
Käytännön seuraus: a program that cannot clear the potency and half-life gates at discovery rarely recovers them Liberty Blue Peptide Synthesizer later, so both belong in the candidate-selection brief alongside peptide stability testing and the permeability plan.
Suullisten ohjelmien analyyttinen karakterisointi
Oral programs must add biorelevant-medium degradant profiling to standard release testing. An analytical package built for an injectable will not characterize the degradants an oral program actually produces.
That means three additions. Ensimmäinen, sequence and modification integrity: confirming the backbone and any non-natural residues survived synthesis intact. Toinen, degradation-product identification in simulated gastric and intestinal media, not just in buffer. Kolmas, counterion and salt-form characterization, since trifluoroacetate exchange affects both assay accuracy and tolerability. Endotoxin testing by LAL assay and a complete certificate of analysis belong in the same package, ja ISO 13485 tai ISO 9001 context tells you whether the supplier’s quality system can support it.
Methods must be validated against the validation characteristics Q2(R2) lähtee liikkeelle, published by the FDA in March 2024. Read those as expectations rather than thresholds: the guideline gives signal-to-noise guidance of roughly 3:1 for detection limit and at least 10:1 for quantitation limit, not peptide-specific cutoffs.
Key Takeaway: A validated peptide analytical characterization package should cover specificity and selectivity, tarkkuus, tarkkuutta Peptidi 2 including repeatability and intermediate precision, alue, response and linearity, havaitsemis- ja määrärajat, and robustness.
This is where a research-grade supplier stops being enough. A 95% purity floor is a conventional research-grade baseline, but it says nothing about which degradants are present or whether the method that measured it was validated for an oral matrix.
Discovery-Stage Synthesis -tarpeet versus kehitys ja laajennus
Discovery and development optimise for different things. Discovery optimises for learning: many analogues, milligram to small research quantities, screening-grade purity acceptable, and turnaround valued over process optimisation. Development optimises for dependable manufacturing: fewer routes, locked and transferable processes, tight impurity control, lot-to-lot comparability, gram-to-kilogram supply, and full analytical and regulatory documentation. The change of optimisation target at scale-up, not the batch size alone, is what breaks programs, as the discovery-to-development framing in Bak et al.’s developability primer sets out (2015).
|
Vaatimus |
Löytö |
Development and scale-up |
|---|---|---|
|
Mittakaava |
Milligram to small research quantities |
Gram to kilogram |
|
Puhtaus tavoite |
Screening grade acceptable |
Tight impurity control, lot-to-lot comparability |
|
Process status Cem Peptide Synthesis |
Many analogues, routes still open |
Fewer routes, locked and transferable |
|
Analyyttinen paketti Peptidi 2 |
Identity and rough purity |
Full characterisation and regulatory documentation |
Peptide scale-up failure modes concentrate in incomplete coupling and deprotection, aggregation and poor resin swelling or mass transfer, thermal gradients, and purification bottlenecks. Small inefficiencies compound across every amino-acid addition, so yield and purity loss from milligram to kilogram scale is real but not reported as a percentage in any primary source, which is why it is described here rather than quantified.
Key Takeaway: Choose your synthesis partner by the stage you are entering, not the stage you are in. A route that tolerates screening-grade purity at milligram scale will not carry a program into gram-to-kilogram supply without process lock and full documentation.
MOL Changes runs custom peptide synthesis from milligram to kilogram scale, asti 200 amino acids and support for 300-plus modifications, and purity from crude through 99 prosenttia. Quality-control methods available include HPLC, LC-MS, endotoksiinien testaus, and sterility testing in a Class 100 puhdastila.
Yleisiä väärinkäsityksiä suun kautta tapahtuvasta peptidin antamisesta
Four beliefs cause most of the expensive failures in oral peptide programs: that a permeation enhancer solves absorption, that oral delivery is a formulation problem rather than a molecule problem, that a stable peptide is a shelf-stable peptide, and that scale-up is simply a bigger batch.
The first two are related. Enhancers act transiently and locally at the intestinal wall, so they widen a window rather than remove the barrier. What changed the outlook for oral peptides was structural modification, which is why formulation alone rarely clears the low single-digit bioavailability ceiling that oral programs run into. If your team is screening excipients before the sequence has been optimised for the gut, the screening is premature.
The third misconception confuses two different measurements. Resistance to gastrointestinal exposure and shelf-life stability are separate properties, and a peptide that survives twelve months on a shelf may still be degraded before it reaches an absorptive surface.
The fourth is a change of target, not of volume. Scale-up shifts what you are optimising for, so a route that works at milligram scale can fail on the parameters that matter later.
⚠️ Varoitus: Oral bioavailability for peptides remains low and variable. No single modification or excipient resolves intestinal permeability. HRS-1596 is an early-stage candidate, and nothing here is an efficacy, turvallisuutta, or approval claim.
Usein kysytyt kysymykset
Minkä oraalisen biologisen hyötyosuuden peptidin tulee olla kehittämisen arvoinen?
There is no single threshold, because the half-life and potency gates interact. A modelling analysis reported in Frontiers in Drug Delivery found that a peptide with a half-life of roughly 24 hours or longer can accumulate meaningfully even at sub-1% bioavailability, while the same analysis places the practical potency ceiling at low-nanomolar EC50. Oral viability is a property of the molecule’s pharmacokinetic profile, not of the delivery technology alone.
Miksi suun kautta otettava semaglutidi on otettava tyhjään mahaan??
Because absorption collapses when food is present. The fasting requirement for oral semaglutide reflects an absolute bioavailability of approximately 0.4-1% under strict fasting conditions, with no more than 4 oz of water, an empty stomach, and a 30-minute fast after dosing, and near-zero absorption with food, as recorded in the FDA clinical pharmacology review and reported in a Frontiers in Drug Delivery review. The instruction is the difference between a therapeutic dose and an ineffective one.
Voivatko läpäisevyyden tehostajat tehdä minkä tahansa peptidin suun kautta saataville?
Ei. Enhancers such as SNAC work by creating transient defects in the intestinal membrane that let the co-formulated peptide cross, and that mechanism is local, short-lived, and payload-specific. An enhancer that carries one peptide across the epithelium will not necessarily carry another, and raising the dose runs into gastrointestinal tolerability limits. Permeation enhancement widens the window for a candidate that already has the right potency and half-life; it does not make an arbitrary peptide absorbable.
Mitä stabiilisuustestausta suun kautta otettava peptidiohjelma tarvitsee, mitä ruiskeena annettava ohjelma ei?
An oral program needs stability data generated in gastrointestinal-relevant media, not just in buffer. Injectable programs characterise the peptide in formulation buffer and plasma; oral candidates additionally have to survive gastric acid, pepsin, and intestinal proteases, so peptide stability testing has to model those conditions rather than assume them. That means proteolytic stability assays in simulated gastric and intestinal fluid, and release methods that reflect the intestinal environment the capsule actually encounters.
Miten löytövaiheen ja kehitysvaiheen puhtausvaatimukset eroavat toisistaan??
Discovery work tolerates crude to 95% puhtaus, because the question being asked is whether the sequence behaves, not whether it can be filed. Development and scale-up work moves toward 99% purity with a documented analytical package, since the same material has to support toxicology, kliininen tarjonta, ja sääntelyn tarkistus. A sequence that looks clean at research grade can reveal impurity and stability problems once the purity floor rises.
Mitä Novon ja Hengruin sopimus oikeastaan merkitsee?
It signals that large pharmaceutical companies are willing to pay for oral peptide delivery capability rather than build it. Hengrui’s announcement of the HRS-1596 licence disclosed a deal worth up to approximately $300 million for an oral GLP-1/GIP candidate, with Novo Nordisk taking the development forward. The signal for anyone running an oral program is the structure rather than the headline number: the licensor retained the discovery and early development work, and the partner bought the later-stage capability.
Johtopäätös ja seuraavat vaiheet
Oral peptide delivery moves five decisions earlier and makes them interdependent: sekvenssisuunnittelu, vakauden testaus, permeability strategy, formulation screening and analytical characterization. Change one and the others move with it, which is why the evaluation sequence matters more than any single modification. A candidate that survives fasted-state intestinal media but fails the developability gate is not a near-miss; it is a program that needed the permeability question answered before the synthesis scale changed.
That is also where the stage distinction earns its keep. Discovery work tolerates crude material and rapid iteration, while development and peptide scale-up demand documented purity, validated methods and batch-to-batch consistency. The handoff points between those stages, not the individual steps, are where programs lose time.
The HRS-1596 licence announced on 29 syyskuu 2026 is one signal in a broader shift: delivery capability, not receptor potency alone, is becoming the differentiator. HRS-1596 is disclosed as phase I-ready for once-weekly oral dosing, and no efficacy or approval claim follows from that disclosure. Oral bioavailability remains low and variable, and no single modification or excipient resolves permeability on its own.
If you are scoping an oral candidate, the useful next step is a capability conversation: talk to an expert about which stage your sequence sits at and what the data package needs to show.
Tietojen paljastaminen: MOL Changes provides custom peptide synthesis services. This article discusses research-stage and clinical-stage peptide development and is not medical advice; consult a qualified professional before making medical decisions.