
Qué significan las “señales neuropsiquiátricas de tirzepatida” en farmacovigilancia

Una señal de farmacovigilancia es una asociación observada., de una o más fuentes, lo que sugiere una asociación causal potencialmente nueva que merece investigación. La existencia de una señal no establece por sí misma la causalidad. (Comunicación de la FDA sobre la seguridad de los medicamentos, 2026-01-13). Esa única frase resuelve la mayor parte de la confusión en torno a las señales neuropsiquiátricas de tirzepatida.: la frase nombra un fenómeno informativo, no es un mecanismo.
Piense en una alarma de humo. Reporta humo. No te dice si la fuente es un incendio., tostada quemada, o vapor de una ducha. Una señal es la alarma.; La evaluación de causalidad es la investigación que sigue..

Tres términos llevan el resto de este artículo.. Desproporcionalidad Mide si un par fármaco-evento aparece en una base de datos de informes con más frecuencia de lo esperado por casualidad.. Generación de hipótesis Describe evidencia que puede plantear una pregunta pero no puede responderla.. Confusión por indicación significa la condición que se está tratando, no la droga, impulsa el resultado.
Las categorías de causalidad de la OMS-UMC dan a esa investigación un vocabulario. La escala abarca seis niveles.: cierto, probable o probable, posible, improbable, condicional o no clasificado, e inevaluable o inclasificable, calificado según una relación de tiempo plausible, explicaciones alternativas, respuesta al retiro, y si se realizó una nueva provocación (Sistema OMS-UMC para la evaluación estandarizada de causalidad de casos, 2021). La brecha entre esos niveles es donde realmente vive el mecanismo generador de hipótesis versus el establecido.. Una calificación de “cierta” no requiere una mejor explicación además de un evento farmacológico o fenomenológico definitivo.; "posible" permite explícitamente una explicación alternativa y falta información de retiro (Criterios de evaluación de la OMS-UMC, 2021).
Conclusión clave: Una señal es una asociación que merece investigación.. No establece causalidad, y leerlo como mecanismo es el error más común en esta literatura..
Por qué la señal se lee como causal cuando no lo es
Tres mecanismos hacen que una señal de tasa de notificación parezca causal incluso cuando no lo es: no hay denominador de exposición, La propensión a informar difiere entre medicamentos y pacientes., y la indicación en sí confunde el resultado. Las medidas de desproporcionalidad evalúan la presentación de informes, no incidencia, por lo que un resultado de desproporcionalidad no puede indicar cuántas personas estuvieron expuestas, solo cuantos informes llegaron. Los informes diferenciales distorsionan aún más la comparación, porque un fármaco más nuevo o más discutido atrae más atención de pacientes y médicos que un comparador más antiguo.
El análisis de tirzepatida de FAERS muestra hasta qué punto un recuento de informes puede estar lejos de una señal. Al otro lado de 37,827 informes de eventos adversos presentados entre abril 2022 y marzo 2024, la clase de órganos del sistema de trastornos psiquiátricos celebrada 1,219 informes de casos, sin embargo, su ratio de probabilidades de presentación de informes era 0.31 (95% CI 0.29 a 0.33), por debajo de cualquier umbral de señal positiva (Análisis de tirzepatida en el sistema de notificación de eventos adversos de la FDA, 2024). La señal de la encefalopatía de Wernicke de 15 casos va en sentido contrario: 15 casos, 14 de ellos de 2023 a 2024, produjo un odds ratio de informe de 2.35 (95% CI 1.38 a 4.01) (Agonistas del receptor GLP-1 y encefalopatía de Wernicke, 2025). Los recuentos pequeños pueden cruzar el umbral porque los métodos frecuentistas de desproporcionalidad son propensos a señales falsas positivas cuando los recuentos de informes son bajos..
Entonces, ¿qué significa eso para la notificación de eventos adversos psiquiátricos GLP-1?? Un recuento grande no es un riesgo, y una pequeña cuenta no es ruido. El número le informa sobre el comportamiento de denuncia, no sobre lo que hace la droga.
Leer los estudios de desproporcionalidad sin sobreleerlos
Los dos análisis de desproporcionalidad que aparecen a continuación generan hipótesis., no confirmatorio: detectan patrones de notificación en datos espontáneos, y ninguno establece incidencia, causalidad, o un mecanismo.
La primera capa es la Serie de casos psiquiátricos de EudraVigilance, que proyectado 31,444 informes recibidos entre 2021-01-01 y 2023-05-30. Eventos adversos psiquiátricos representados 372 informes, o 1.18%. Tirzepatida apareció en 740 informes (2.3%), de los cuales 15 eran psiquiátricos: ansiedad en 13 (86.7%), depression in 4, suicidal ideation in 4, and no fatal outcomes. The EudraVigilance suicidal-event breakdown from the same dataset counted 102 suicidal events overall, with tirzepatide accounting for 4 (3.9%), cual es 26.7% of its 15 psychiatric reports.
The second layer asks a different question. El 2026 EudraVigilance reporting-pattern analysis proyectado 76,847 ICSRs, retained 42,941 eligible ones, and found suicide- or self-injury-related events in under 0.3% de ellos. Tirzepatide accounted for 47 casos, contra 141 for semaglutide and 37 for liraglutide, with no fatal tirzepatide cases and suicidal ideation in 85.1% de ellos. Against tirzepatide as comparator, the reporting odds ratios were 2.54 (1.60–4.01) for liraglutide and 2.69 (1.91–3.83) for semaglutide.
That inversion is the point: reporting odds ratios are only interpretable against the exposure base, so the same database supports a molecule-shaped story or a class-shaped one depending on which comparator is chosen.
|
Study |
Dataset and period |
norte |
Comparator |
Estimate |
What it can establish |
What it cannot |
|---|---|---|---|---|---|---|
|
Psychiatric ICSR analysis (2024) |
EudraVigilance, 2021-01-01 a 2023-05-30 |
31,444 informes; tirzepatide 740, psychiatric 15 |
Descriptive proportions |
Psychiatric AEs 1.18% of reports; tirzepatide psychiatric 15 |
Síntesis química en fase sólida That psychiatric reports exist and how they cluster by reaction term |
Incidence, causality, or a rate per exposed patient |
|
Suicidal-event breakdown (2024) |
Same EudraVigilance dataset |
102 suicidal events; tirzepatide 4 |
Descriptive proportions |
tirzepatida 3.9% of suicidal events; 26.7% of its psychiatric reports |
The internal composition of tirzepatide’s psychiatric reports |
Comparison against other drugs without a shared denominator |
|
Reporting-pattern analysis (2026-08-27) |
EudraVigilance, 76,847 proyectado, 42,941 eligible |
tirzepatida 47 casos |
ROR versus tirzepatide |
Liraglutide 2.54 (1.60–4.01); semaglutide 2.69 (1.91–3.83) |
That reporting odds differ between molecules under a stated comparator |
Causation; RORs are not incidence rates |
Nota: the AACE/VigiBase figures (18 informes; semaglutide ROR 10.2; tirzepatide ROR 11.4) come from a different dataset and must never be averaged with the EudraVigilance figures above.
Lo que realmente puede descartar la evidencia aleatoria y de cohorte

The strongest evidence on tirzepatide and psychiatric harm is not one study but a stack of them, and it points the same way. The FDA ran the FDA’s cross-program meta-analysis across 91 placebo-controlled GLP-1 receptor agonist trials covering 107,910 pacientes (60,338 on drug, 47,572 on placebo), because the FDA’s stated reason for running a cross-program meta-analysis was that individual trials contained too few suicidal ideation and behavior cases to resolve the question alone. The FDA Sentinel cohort then followed 2,243,138 users and found no increased intentional self-harm versus SGLT2 inhibitors. On that basis the FDA’s stated conclusion was that the totality of the studies does not support a causal relationship.
Independent work agrees. The JAMA Psychiatry meta-analysis of 80 ensayos fiestas 107,860 patients and found no significant difference in serious psychiatric adverse events (log RR −0.02; 95% CI −0.20 to 0.17; P = .87). The pooled SURMOUNT psychiatric safety analysis de 4,056 participants reported PHQ-9 scores of 15 or above in 1.2% on tirzepatide versus 2.3% on placebo (O 0.47; p = 0.004), with suicidal ideation or behavior at 0.6% in both arms. The TriNetX active-comparator cohort matched 85,546 tirzepatide and semaglutide pairs and found a Year-1 composite psychiatric outcome of 7.0% versus 7.1% (HR 0.984; 95% CI 0.950 a 1.019). The Year-2 anxiety estimate was nominally higher (HR 1.052; 95% CI 1.001 a 1.106), though the authors did not adjust for multiple comparisons.
Here is the boundary that decides how far any of this generalizes. The SURMOUNT psychiatric exclusion criteria excluded anyone with a lifetime suicide attempt, active or unstable major depression, or severe psychiatric illness within two years, and why SURMOUNT-4 was excluded from the pooled analysis is instructive: every enrollee received open-label tirzepatide before randomization, so the pooled dataset cannot speak to people with prior psychiatric exposure. The trial counts also differ by source, 80 in the JAMA Psychiatry review and 91 in the FDA’s, and that discrepancy is worth stating rather than resolving. For evidence quality in pharmacovigilance signals, the honest reading is that these datasets rule out a large causal effect in the populations studied, not that they clear the drug everywhere.
Por qué la elección del comparador decide qué significa una señal
Péptido cíclico A signal claim without a named comparator is not a claim. The same drug, the same database, and the same outcome can point in opposite directions depending on what the exposed group is measured against, and that is exactly what happened with GLP-1 receptor agonists.
In one TriNetX cohort, tirzepatide was compared with semaglutide and produced a psychiatric signal. In the same cohort, semaglutide compared with other GLP-1 RAs produced the reverse: a composite psychiatric outcome hazard ratio of 0.866 (95% CI 0.832–0.901) in Year 1, depression HR 0.811 (0.770–0.855), and suicidal ideation HR 0.488 (95% CI 0.339–0.702), according to the semaglutide-versus-other-GLP-1-RA comparison in the same cohort. The direction flipped because the comparator changed, not because the drug changed.
The EudraVigilance reporting-odds result is the second instance: tirzepatide returned the lowest reporting odds of the three agents examined, again a function of what it was measured against.
|
Comparison |
Direction |
What changed |
|---|---|---|
|
Tirzepatide vs semaglutide |
Signal present |
Comparator: semaglutide |
|
Semaglutide vs other Orden de péptidos GLP-1 RAs |
Protective (HR 0.866) |
Comparator: other GLP-1 RAs |
|
EudraVigilance reporting odds |
Tirzepatide lowest |
Comparator: spontaneous-report N Terminal Modification base |
What makes the TriNetX comparison worth taking seriously is its design. It used the design features that make an active-comparator comparison credible: a new-user active-comparator structure, a 12-month washout, a 30-day lag to mitigate protopathic bias, landmark analysis, and two prespecified negative control outcomes. Even so, the authors state that residual confounding cannot be entirely excluded.
Para propina: Before accepting any signal claim, ask which comparator and which database produced it. A finding without both is not yet evidence quality in pharmacovigilance signals.
What Peptide Characterization Decides About a Study’s Signal
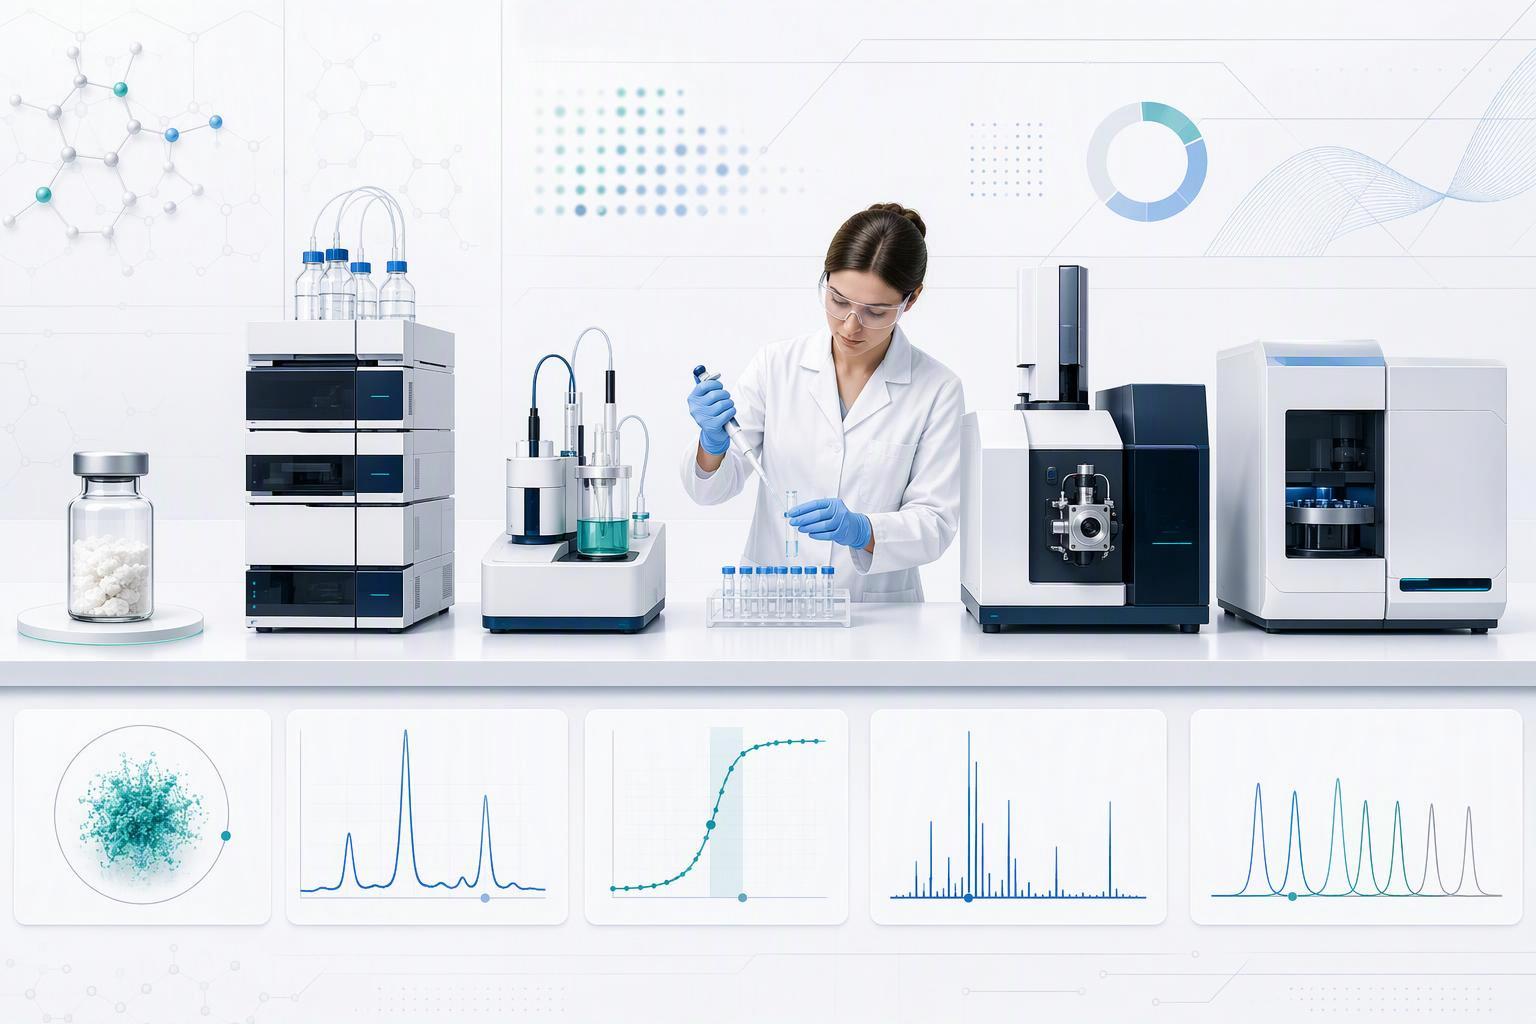
A study does not test a molecule. It tests the material in the vial, and the label on that vial rarely states how much of it is peptide.
That distinction is the whole of this section’s argument. HPLC purity is not peptide content. A lyophilized peptide can read 99% pure by HPLC area and still be only 75–85% peptide by mass, with water and counter-ions accounting for 15–25% of the powder (Modern Analytical, Complete Guide to Peptide Testing, recuperado 2026-07-22). Area percent describes the chromatogram; peptide content describes the weighed material. Area percent is blind to non-UV-absorbing species, to co-eluting impurities behind one peak, and to how much of the powder is peptide at all. Proveedor de péptidos C Terminal Modification 2
The gap matters because it changes the exposure the study actually tested. A batch dosed by weight on an area-percent figure delivers less peptide than the protocol assumes, and any signal that follows is attributed to the wrong exposure.
Orthogonal characterisation is the standard answer: LC-MS confirms intact mass against the theoretical mass derived from sequence, Karl Fischer quantifies water, and amino acid analysis gives peptide content by mass. For a 39-residue synthetic peptide with a C-terminal amide and a branched C20 fatty-diacid side chain on one lysine, el 2026 FDA draft guidance on analytical procedures for synthetic peptides points to high-resolution MS with fragmentation analysis, while ICH Q2(R2) sets general validation expectations that are not peptide-specific.
MOL Changes supports orthogonal analytics and documented sterility and endotoxin control, which can be used to keep peptide characterization and study controls traceable across a batch record.
Las comprobaciones operativas que separan una señal de un artefacto
Run any tirzepatide neuropsychiatric claim through six questions before you repeat it. Which evidence class is this: spontaneous report, disproportionality analysis, cohort study, or randomized trial? What is the comparator, and is it placebo, an active GLP-1, or the general population? What is the exposure denominator, meaning how many people were actually taking the drug and for how long? Which population was excluded, particularly people with pre-existing psychiatric diagnoses? Was the psychiatric outcome prespecified in the protocol or extracted after the fact? And what does the batch documentation show about the material that was actually administered?
The social-media listening analysis of GLP-1 side effects fails the control and direction checks outright. That study screened 12,136 Reddit comments, 14,515 YouTube videos, y 17,059 TikTok videos across 5,859 threads, finding 353 anxiety and 204 depression keyword matches, with bidirectional effects reported in the same population (GLP-1 Receptor Agonists and Related Mental Health Issues, 2023). Self-reported, unverified posts cannot separate a drug effect from the reason someone started the drug.
⚠️ Advertencia: A source that fails the control and direction checks, like social listening, cannot establish either risk or benefit.
Peptide characterization and study controls belong on the same checklist, because an unreported batch leaves the exposure itself undefined. Commercial interest deserves the same scrutiny: check who funded the analysis before you cite it.
Hacia dónde se dirige la evidencia y hacia dónde aún es escasa
The tirzepatide neuropsychiatric signals literature is moving in one clear direction: toward study designs that include the people most likely to be affected rather than screening them out. Three changes would do the most to move it.
Primero, cohorts that include rather than exclude prior psychiatric illness. Excluding those participants removes the subgroup where an effect would be most visible, so a null result in an excluded population says little about risk. Segundo, prespecified psychiatric endpoints, registered before data collection, so a finding cannot be selected after the fact from a broad adverse-event list. Tercero, characterization reporting detailed enough that a reader can reconstruct the exposure: what the peptide was, how it was measured, and what the batch documentation showed.
Where the evidence is still thin, it is thin in ways that matter. There is no mechanism work establishing a pathway, so the biology remains a hypothesis rather than an explanation. No trial has been powered for the highest-risk groups, which means the absence of a signal in those trials is not evidence of absence. And the cohort results split genuinely between negative and positive findings, a disagreement that reflects different populations and endpoints rather than one study echoing another.
Conclusión clave: The evidence base is moving toward inclusion of higher-risk populations, and characterization reporting is what makes those results reconstructable. Until both arrive, the honest reading stays conservative: evidence suggests an association, and no more than that.
Preguntas frecuentes
¿Qué es una señal neuropsiquiátrica de tirzepatida?, ¿Y significa que la droga causa el evento??
No. A pharmacovigilance signal is a statistical flag that a reported event appears more often than expected in a database, not a finding that the drug caused it. Disproportionality measures reporting patterns, and reported events are unverified, so a signal opens an investigation rather than closing one.
¿Por qué la FDA eliminó la advertencia de suicidio?, y que establece eso?
The removal reflects a review that did not find the evidence strong enough to keep a class warning in place, not a finding that no association exists. It means regulators judged the available data insufficient to support the warning, which is a statement about evidence strength rather than about biological risk.
¿La tirzepatida transmite una señal neuropsiquiátrica más fuerte que la semaglutida??
The published disproportionality comparisons do not establish a clear ranking between the two. Reporting rates differ by indication, launch timing, media attention and prescribing volume, so a higher reported rate for one agent is not evidence that it carries more risk.
¿Por qué el ROR de la encefalopatía de Wernicke es 2.35 no hay evidencia de causalidad?
A reported odds ratio of 2.35 describes how often that event was reported relative to other drugs in the database, not how often the drug produced it. Spontaneous reports are unverified, subject to stimulated reporting, and lack a denominator of exposed patients, so the figure cannot support a causal claim.
¿Se aplican los resultados agrupados del ensayo a alguien con antecedentes psiquiátricos??
The pooled analyses generally excluded or underrepresented people with active psychiatric illness, so their results cannot be extended to that group. Absence of a signal in a trial population is not evidence of safety in a population the trial did not study.
¿Qué documentación debo pedir a un proveedor antes de realizar un estudio??
Ask for the batch-specific certificate of analysis, the analytical method used, and the orthogonal confirmation data behind the identity claim. Method principle matters more than a headline purity figure: an HPLC area percent and a peptide content by mass answer different questions, and only the second tells you how much peptide the vial contains.
Conclusión
The lesson from tirzepatide’s neuropsychiatric reporting is not that the signal is real or that it is noise. It is that three things decide what any signal means: the evidence class it comes from, the comparator it was measured against, and whether the material studied was characterized well enough to support the comparison at all. Move up that ladder, from spontaneous reports through disproportionality analyses to randomized and cohort data, and the range of explanations narrows. Change the comparator, and the same numbers can point in a different direction. Skip the characterization work, and a study can generate a signal about an impurity rather than a molecule.
That framework travels well beyond this one drug. As trials and cohorts extend into higher-risk populations, the tirzepatide neuropsychiatric literature will keep testing it, and the reporting will keep arriving faster than the mechanism evidence.
If you work with these data, the practical next step is documentation: request the analytical package and review the CoA template before you compare one batch’s results to another’s.
Anyone weighing a medication decision should consult a qualified healthcare professional.





