What Operation TrialBlazer Actually Changes for Peptide CRO Selection for Phase 1
Operation TrialBlazer peptide development changed on September 15, 2026, when the FDA opened applications for the Expedited IND Pilot, the agency-run program inside HHS’s broader TrialBlazer initiative (the FDA’s Expedited IND Pilot announcement, 2026-09-15). The program is open for applications until 11:5910月東部時間午後 30, 2026, and FDA expects to select 8–10 sponsor–QRI pairs for the initial cohort (the application deadline, content current 2026-09-21).

The mechanism is sequencing, not leniency. Qualified research institutions bring specialized scientific expertise into IND preparation, which lets FDA review and accept individual components on a rolling basis during the pre-IND phase instead of waiting for the complete package (how rolling pre-IND review works, 2026-09-15). FDA’s stated aim is to catch and resolve issues in real time, reducing the risk of a first-in-human clinical hold (the pilot’s stated purpose, 2026-09-15). FDA retains full regulatory authority throughout, including the decision to impose a clinical hold (FDA retains full regulatory authority, 2026-09-15).
重要なポイント: The pilot changes when components are reviewed, not what is expected of them. FDA removed several Phase 1 CMC obligations (what FDA actually expects in a Phase 1 CMC section, content current 2026-06-22), so the bar that actually rises is on partner capability and on defending phase-appropriate methods in a live rolling dialogue (the bar that actually rises, 2026-06-18 に 2026-09-21).
That distinction is the whole basis of peptide CRO selection for Phase 1 under this program.
4つの基本速度は緩まない
Operation TrialBlazer changes review sequencing, not the assurance standard. FDA’s phase-appropriate CMC doctrine holds that “sufficient information should be submitted to assure the proper identification, 品質, 純度, そして治験薬の強さ,” with the amount varying by phase, 配合, and study duration (FDA CMC for INDs, 取得した 2026-06-22). That is why the fundamentals do not move: the four assurance attributes FDA names are identification, 品質, 純度, そして強さ, and the CMC component covering drug substance, drug product, placebo, and labeling still applies at Phase 1. What “right-sized” permits is less data, not weaker evidence. Note the record’s limit: FDA’s minimum-information clarification is written for small-molecule and recombinant biological products, and no peptide-specific Phase 1 CMC sub-page was found on FDA’s site, so peptide sponsors should read the doctrine as a principle and confirm specifics with CDER.
|
Fundamental |
Evidence artifact that demonstrates it |
Named standard |
|---|---|---|
|
Identification |
Orthogonal confirmation, for example mass spectrometry plus amino acid analysis |
I Q2(R2) |
|
品質 |
Batch records and release testing traceable to source data |
MHRA ALCOA principles |
|
純度 |
Impurity profile resolving truncations, エピマー, and degradation products |
I Q2(R2) |
|
Strength |
Peptide content assay with defined counter-ion basis |
USP monographs where applicable |
テーブル: 段階 1 peptide CMC requirements mapped to the artifact that demonstrates each.
チップ用: Scope stability to the Phase 1 study duration and actual storage conditions rather than a default long-term program.
How to Evaluate a Peptide CRO’s Identity and Purity Capability
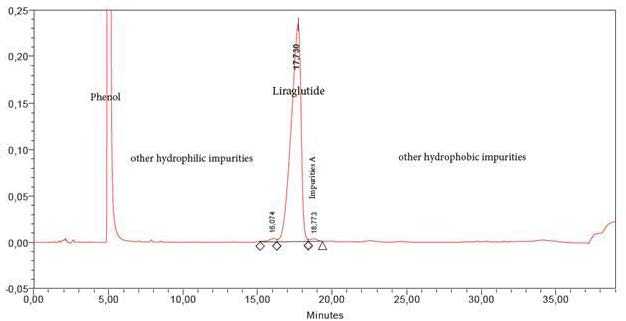
Identity and purity claims are only as strong as the orthogonal methods behind them. Ask whether the package pairs amino acid analysis with HPLC and mass spectrometry, whether impurity profiling separates process impurities from truncations, エピマー, and degradation products, and whether raw chromatograms are supplied rather than summarized. These are the assurance attributes a reviewer checks, and they sit outside what FDA does not expect at first-in-human under the Phase 1 flexibility list.
The concrete artifacts tell you more than any capability statement. Request the certificate of analysis, the full chromatograms, and the method qualification summary, and read them against what thin characterization looks like to a reviewer in FDA’s comparative-peptide-impurity deficiency findings.
A CRO that supplies all three artifacts without being asked is demonstrating peptide identity purity stability testing capability in the only way that counts: documented, method-backed, and inspectable.
安定性を示す方法とフェーズに適した検証を評価する方法
段階 1 flexibility on analytical method validation for peptides is a staging allowance, not a waiver, and it narrows as the program advances. The Phase 1 CMC flexibilities FDA lists state that analytical method validation data, clinical-lot stability data, full-duration stability coverage, and process controls unrelated to safety are not expected at first-in-human. Those items are deferred, not deleted: why the flexibility narrows as the program advances is that the amount of CMC information required tracks the phase, so the same package that satisfies a Phase 1 IND will not carry a Phase 2 ファイリング. FDA’s estimate of reduced application development time puts the Phase 1 benefit at up to 12 月, which is exactly the window a thin method package can consume in rework.
⚠️警告: A method package too thin to answer an FDA question quickly forces rework under a compressed clock, and the 12-month allowance is already spent.
What a sponsor still has to defend is the stability-indicating nature of the method itself: that it separates and quantifies the degradants the peptide actually forms.
エンドトキシンの評価方法, 無菌性, ペプチドの仕様およびリリース仕様
ペプチド合成 Release specifications are where a partner’s real limits surface, usually after you have committed. For a parenteral peptide, the bacterial endotoxin limit is calculated as K/M, where K is the threshold pyrogenic dose per kilogram per hour (5 EU/kg for most parenteral routes) and M is the maximum human dose per kilogram per hour. あ 70 kg patient receiving a 1 mg/kg dose gives M = 1 mg/kg/hr, so the limit is 5 EU/kg ÷ 1 mg/kg = 5 EU/mg. Route changes the arithmetic: intrathecal products use a far lower K, so the same peptide can face a limit orders of magnitude tighter. Sterility expectations follow the same logic, since a sterile injectable requires validated aseptic processing or terminal sterilization with supporting data.
When you screen suppliers, one published vendor scorecard’s red flags are useful as an attributed checklist rather than a benchmark: no peptide-specific references or vague capability claims, fully outsourced analytical testing, recent warning letters or repeat 483 observations, and heavy dependence on a single client for revenue. Treat these as questions to ask, not thresholds to score against.
Building the Decision Matrix for Peptide CRO Selection for Phase 1
Score every candidate on evidence-generation capability, not on how fast it claims to move. A published peptide CDMO scorecard weights synthesis capability highest at 25%, followed by analytical and QC at 20%, regulatory history at 20%, capacity and scalability at 15%, quality systems at 10%, and financial and strategic fit at 10% (Peptide CDMO Selection Criteria, reviewed April 2026). Treat that as an illustrative structure only: the source publishes no methodology behind the weights, and it is not evidence that sponsors weight criteria this way. Set your own weights, then add the row that now outranks everything else.
|
Criterion |
重さ |
Candidate A |
Candidate B |
Candidate C |
|---|---|---|---|---|
|
QRI qualification bar |
Highest |
|||
|
Synthesis capability |
||||
|
Analytical and QC |
||||
|
Regulatory history |
||||
|
Capacity and scalability |
||||
|
品質システム |
||||
|
Financial and strategic fit |
The QRI row carries the highest weight because CROs are explicitly contemplated as qualified research institutions: CDER director Michael Davis told reporters QRIs “could be academic medical centers or contract research organizations” (BioSpace, September 15, 2026). Score that row against what QRI designation requires: demonstrated capabilities, インフラストラクチャー, and leadership expertise across nonclinical, clinical, and CMC disciplines, regulatory affairs, and clinical trials relevant to first-in-human INDs and Phase 1 研究. Note the boundary. QRIs act only as a review and advisory resource, and sponsors remain responsible for their IND submissions.
急ぐスケジュールの下でスポンサーが犯すよくある間違い
The recurring failure under an expedited timeline is reading “phase-appropriate” as “optional.” The flexibilities are real but narrow, and sponsors who treat them as a general waiver absorb the cost later as rework under a compressed clock.
Deferring impurity profiling. Teams under milestone pressure run identity and purity release first and postpone impurity method development. The fix is to profile impurities early enough that the method is ready before the batch is, since a reviewer question about an unidentified peak cannot be answered retroactively.
Overbuilding the stability program. The opposite error: designing a commercial-scope stability package for a Phase 1 candidate. Match the program to the phase and the intended duration.
Shipping a thin method package. A package that cannot answer a reviewer’s question stalls the submission. Treat analytical method validation for peptides as the deliverable, not the paperwork around it.
Treating the QRI as a transfer of responsibility. Sponsors remain responsible for their submissions; a qualified research institution acts as a review and advisory resource.
What Success Looks Like at the End of Peptide CRO Selection
Success in peptide CRO selection for Phase 1 is a partner whose documentation answers a reviewer’s question without a second round. You should be able to request the full artifact list, receive it in one response, and hand it to a regulatory reviewer without chasing missing pieces.
The verifiable signals map to the capability bar a qualified partner clears: methods qualified to the phase you are in, stability scoped to the study rather than to a generic shelf-life claim, and a named regulatory contact who answers technical questions directly instead of routing them through a sales channel. That last signal matters most when your IP is the asset at risk, because a named contact shortens the communication loop and reduces how many people touch your sequence. ペプチドの生産
MOL Changes illustrates what a documentation-complete peptide package looks like: a CoA, HPLC chromatogram, and MS spectrum with every order, analytical HPLC for purity, ESI-MS or MALDI-TOF for identity, and amino acid analysis for content, produced in a Class 100 ultra-high sterile clean room at milligram-to-kilogram scale. Note that this is analytical capability, not regulatory-affairs support; the knowledge base does not substantiate IND-filing services, so treat that as a separate evaluation criterion.
Commercial disclosure: MOL Changes はペプチドの品質基準に商業的関心を持っています.
Ready to evaluate a documentation-complete peptide package? Request a peptide characterization consultation and bring your artifact checklist to the conversation.
よくある質問
Can I still apply to the Expedited IND Pilot after October 30, 2026?
いいえ. The application window closes October 30, 2026 で 11:59pm ET, and FDA has published no second cohort or extension. If you are weighing Operation TrialBlazer peptide development for a Phase 1 program, the practical question is not whether to apply but whether your CMC package can be assembled before that date. Sponsors who cannot meet it should plan for the standard IND pathway rather than assume a follow-on window will open.
資格のある研究機関と協力することにより、IND の責任が移転されますか?
いいえ. QRIs advise; sponsors submit. A qualified research institution acts as a review and advisory resource, and the sponsor remains responsible for the content, 正確さ, and completeness of everything filed. Treat QRI feedback as expert input to your own review, not as a substitute for it, and keep your own record of how each comment was resolved. について
フェーズを実行します 1 分析方法検証の柔軟性はフェーズまで拡張 2?
Not in the same form. The flexibility is phase-appropriate by design and narrows as the program advances, which is why the Phase 1 flexibility does not extend forward unchanged. Analytical method validation for peptides should be planned as a staged commitment, with fuller validation data expected as you approach later phases. Confirm current expectations with FDA before you lock your Phase 2 plan.
くも膜下腔内ペプチドのエンドトキシン制限はどのように変化しますか?
The limit is route-dependent, calculated as K divided by M, where K is the threshold pyrogenic dose and M is the maximum human dose per kilogram per hour. Because an intrathecal dose is far smaller than an intravenous one, the permitted endotoxin limit is correspondingly tighter. Set the specification from your own maximum dose and route, and confirm the calculation with your analytical team before release testing.
結論
PhaseのためのペプチドCRO選択 1 under Operation TrialBlazer comes down to one reframe: the pilot shortens the timeline, not the evidence a reviewer will ask for. A partner who can generate identity, 純度, 安定性, and release data that stands on its own is worth more than one who promises the fastest calendar, because the second round of questions is where expedited programs lose their advantage. Score every candidate on the same question: when a reviewer challenges an impurity profile, a stability-indicating method, or an endotoxin limit, can this partner answer with documentation already in hand? Use the decision matrix from this guide to weigh that capability against cost and timing, and start the conversation with your shortlist before the October 30, 2026 window closes.