
Hur oral peptidutveckling bedöms: kriterierna som avgör jämförelsen
Oral peptidutveckling bedöms utifrån fem kriterier, och samma fem avgör varje senare avsnitt av denna jämförelse: stabilitet, permeabilitet, doskonsistens, nedbrytning och föroreningskontroll, och jämförbarhetsbevis. De två alternativen här är bevispaket, inte leverantörer. En är den muntliga kandidaten; den andra är den injicerbara kontrollen den skulle behöva förskjuta.
Utgångspunkten är basräntan. PK-gränsöversikten rapporterar att oral biotillgänglighet för peptider avsedda för systemisk verkan vanligtvis är lägre 1% även under optimerade förhållanden, mot ungefär 10-25% för pulmonell insulintillförsel. Dosmultiplikationsarithmetiken för sub-1 % biotillgänglighet följer direkt: a 0.4-1.0% absolut band med betydande inter- och intra-subjekt variabilitet driver orala doser upp med faktorer av 10 till 100.
Den siffran uppmanar till en andra fråga, om litteraturen visar hur ofta program misslyckas. Det visar det inte tillförlitligt. Komplexitetsrecensionens varning för publicering-bias är explicit: misslyckanden och avbrutna program är systematiskt underrapporterade, så misslyckade program kan inte med säkerhet räknas från den publicerade posten.
Key Takeaway: Bedöm en muntlig kandidat på stabilitet, permeabilitet, doskonsistens, nedbrytning och föroreningskontroll, och jämförbarhetsbevis. På aktuella bevis, ingen oral kandidat bör behandlas som utbytbar med dess injicerbara kontroll.
Snabb jämförelse: vad varje alternativ har att visa
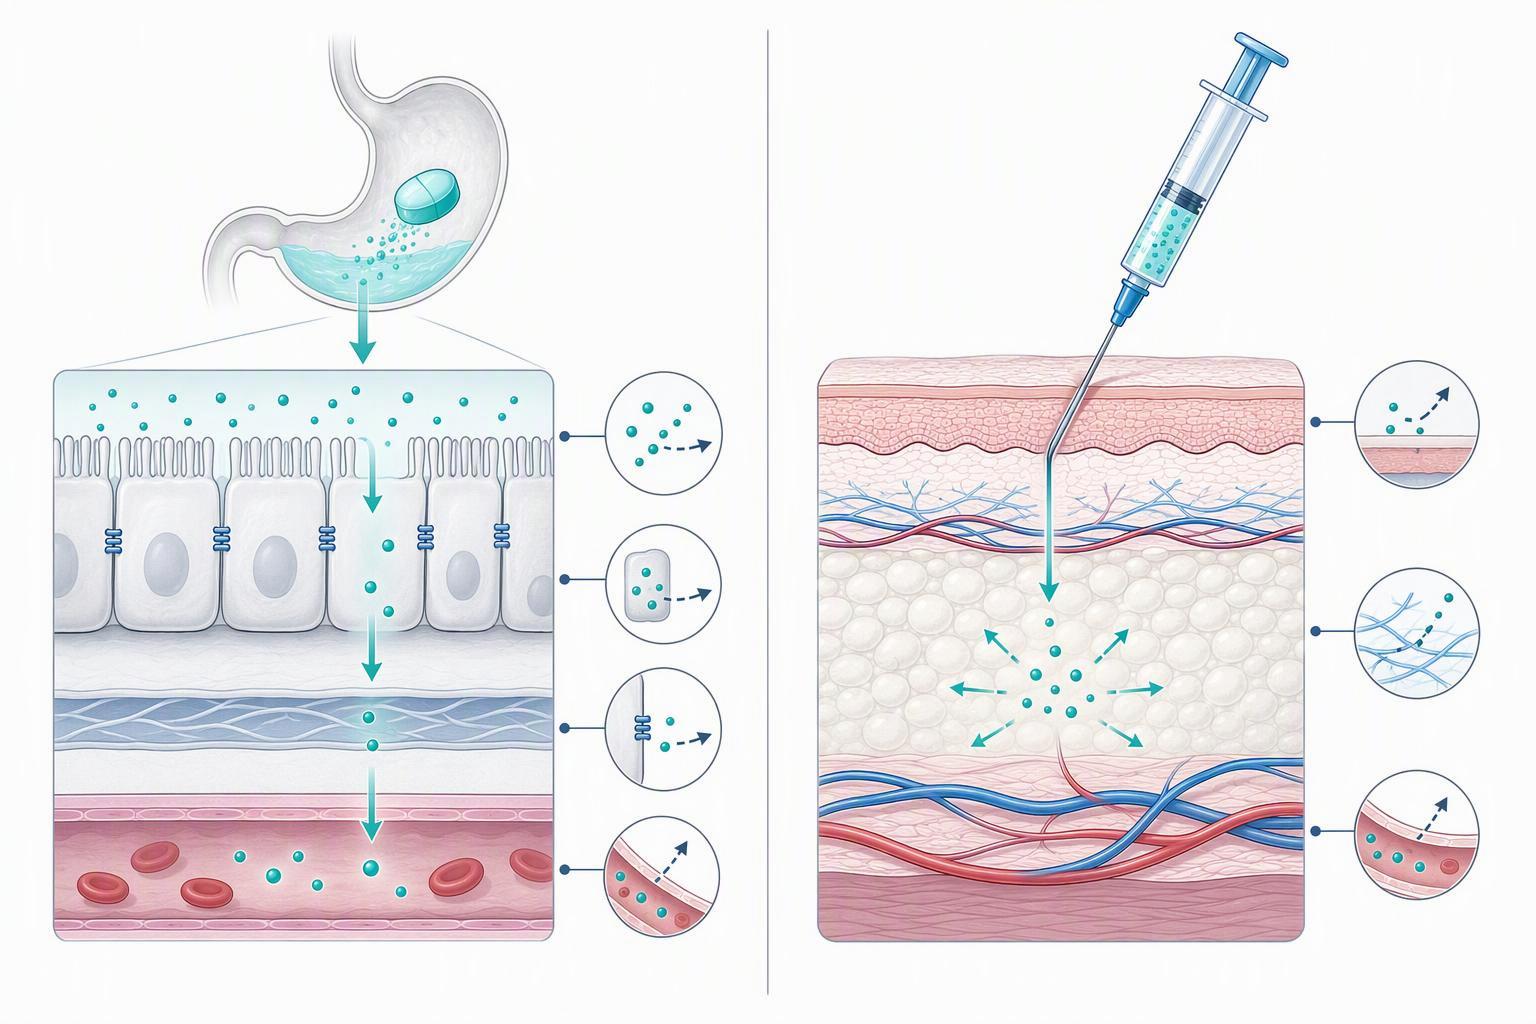
Jämförelsen av orala kontra injicerbara peptider är inte en fråga om preferens. Det är en fråga om vilka bevis varje väg kan producera, och hur mycket av det tillsynsmyndigheter och granskare kommer att acceptera.
|
Beviskrav |
Muntlig kandidat |
Injicerbar kontroll |
|---|---|---|
|
Absorptionsväg |
Över mag- och tarmepitel, med en permeationsförstärkare |
Direkt subkutan eller intramuskulär deposition |
|
Krav på fasta |
Obligatorisk. Alla nuvarande orala peptidformuleringar kräver fasta, och dosering med mat resulterar i nästan noll biotillgänglighet (Gränser i drogleverans, 2026) |
Ingen |
|
Dosmultiplikation |
Vanligtvis 10–100 gånger den injicerbara dosen för att nå jämförbar exponering |
Referensdos |
|
Exponeringsvariabilitet |
Bredare Cmax och tmax spridning; mateffekt kan minska absorptionen med ungefär 90% (Mycapssa förskrivningsinformation, Avsnitt 12.3, etiketten reviderad 2025-07-24) |
Stram, injektionsstyrd |
|
Innehållslikformighet börda |
Hög: varje enhet måste passera beräkningen av USP-acceptansvärde |
Lägre, en enhetspresentation |
|
Jämförbarhetsbevis |
Kräver överbryggande exponering, fastande tillstånd, och mateffektdata till injicerbaren |
Etablerad referensprofil |
Dos-multiplikationsraden är där jämförelsen vanligtvis vänder. I Mycapssa-etikettens endosjämförelse, 20 mg oral oktreotid gav systemisk exponering liknande 0.1 mg subkutan oktreotid, med Cmax 33% lägre och tmax på 1,67–2,5 timmar kontra 0.5 timmar.
Varje rad ovanför blir ett utvärderingskriterium i avsnitten som följer.
Stabilitet: vilket alternativ håller sin styrka under hållbarhetstiden?
Den injicerbara kontrollen vinner på stabilitet idag, och det vinner av en strukturell anledning: dess peptid behöver bara överleva lagring, medan en oral kandidat måste överleva lagring och sedan mag-tarmkanalen.
Det är tre separata fellägen, inte en. Kemisk stabilitet täcker peptidens ryggrad och sidokedjor. Proteolytic stability covers what gastric and intestinal enzymes do to the sequence after dosing. Excipient compatibility covers interactions between the peptide and everything formulated around it. A candidate can pass the first and fail the second, which is why a clean release profile says little about oral viability.
The probe set for the chemical question is established. De I Q1A(R2) stress-testing matrix specifies temperature in 10 °C increments above accelerated conditions, humidity where appropriate, oxidation, photolysis, and hydrolysis across pH, and requires that the analytical methods separate the API from its degradants. Oxidation, deamidering, hydrolysis and aggregation are the pathways that matrix is designed to expose.
Nyansen spelar roll: an injectable is not automatically stable. It carries cold-chain limits and its own aggregation risk. But its stability question stays a storage question. The oral candidate’s does not. De calcitonin failure analysis shows how that gap closes a programme: insufficient gastric absorption, plasma concentrations at the limit of detection, and fibrilization-driven potency loss.
Permeabilitet: vilket alternativ får peptiden över barriären intakt?
The injectable control wins this criterion outright, because it never has to cross the intestinal barrier at all. Permeability is the single largest source of the oral candidate’s dose penalty: class-wide oral bioavailability for peptides sits below 1% in most cases, som dokumenterats i the PK-boundaries review, which is why oral peptide formulation strategies revolve around permeation enhancers rather than around the peptide itself.
How those enhancers work is now better characterised. A 2025 study in Naturkommunikation traced SNAC’s two-stage mechanism: it associates with the peptide in the aqueous layer and monomerizes it as a surfactant, then neutralizes and inserts into the lipid bilayer, forming dynamic SNAC-filled membrane defects through which the peptide sinks, in the authors’ phrasing, “analogous to quicksand,” with membrane integrity maintained afterwards. The route is transcellular, not paracellular.
The effect sizes remain modest and unstable. The tabulated enhancer effect sizes show C10 with LMWH at 3.9–7.6% relative, desmopressin at 2.4% relative to subcutaneous against roughly 0.2% for the marketed tablet, ISIS 104838 på 9.5% relative with an intra-subject range of 2–28%, and insulin tregopil at 1.5–2.0%. The same review notes massive intra-subject variability across all studies, so single-enhancer fixes for peptide stability and permeability are not supported by the clinical record.
Doskonsistens: vilket alternativ ger en förutsägbar exponering?
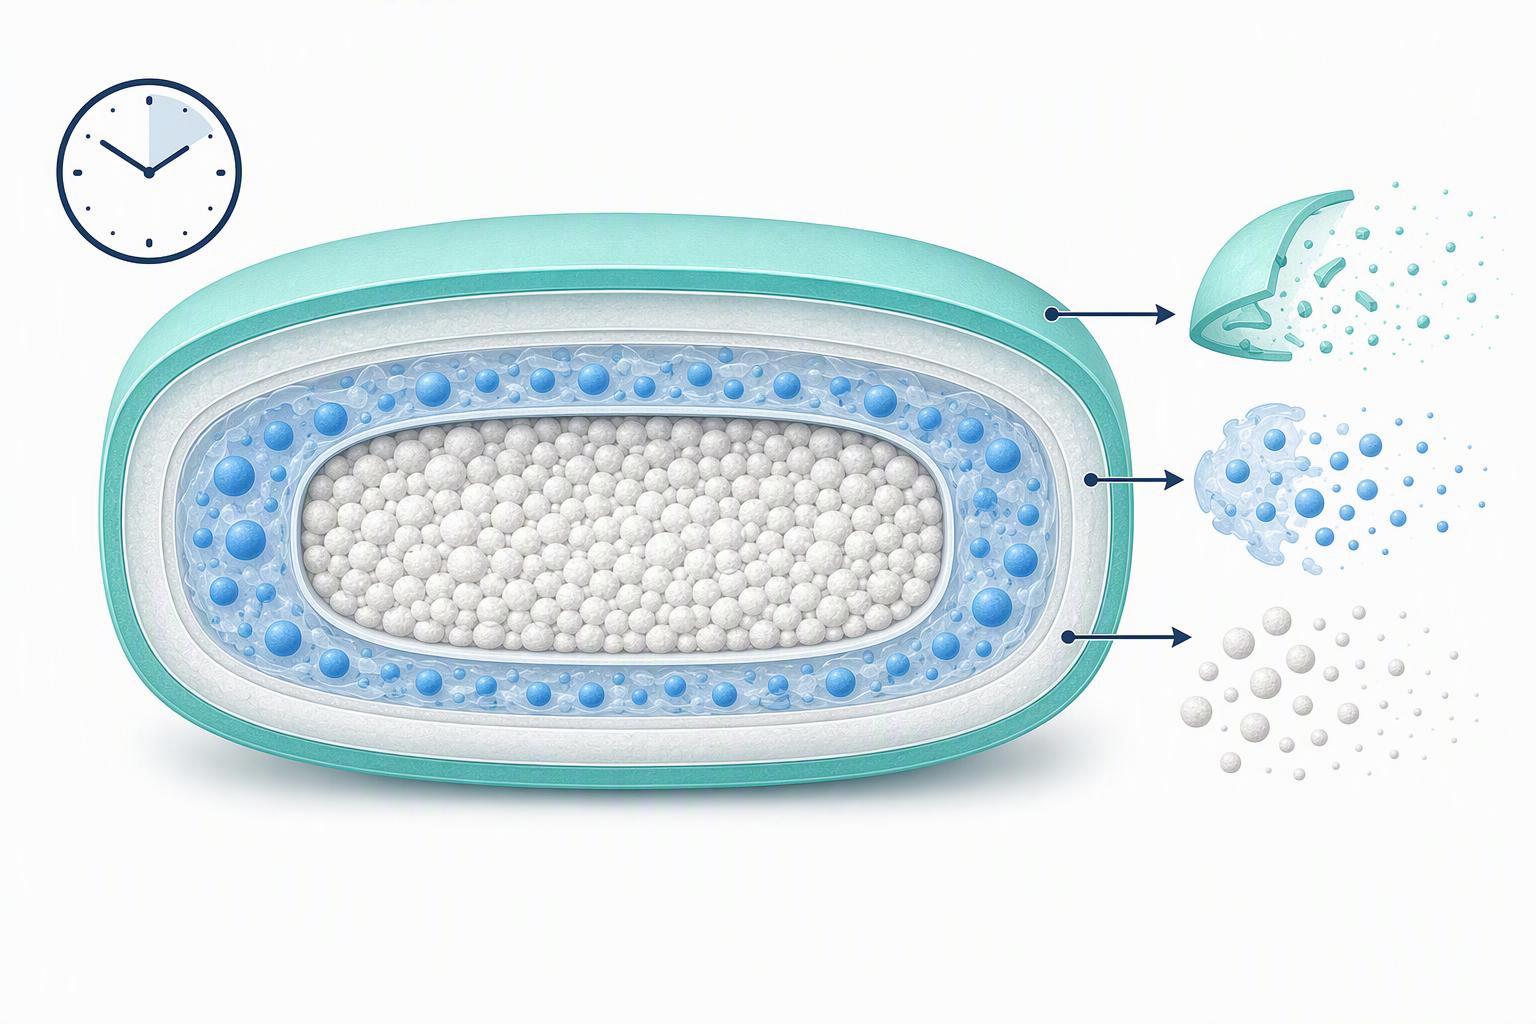
The injectable control wins on dose consistency, and the gap is structural rather than a matter of better manufacturing. A tablet can pass compendial content-uniformity testing and still deliver a variable absorbed fraction, because two independent sources of variance sit between the label claim and the systemic exposure.
The arithmetic behind that claim is the USP acceptance-value calculation, which sets AV = |M − X̄| + ks, with k = 2.4 for n = 10 och 2.0 for n = 30, T = 100.0% by default, M = X̄ when X̄ falls between 98.5% och 101.5%, AV ≤ L1 = 15.0, and no unit outside L2 = 25.0% deviation from M (USP General Chapter <905>). Passing that test constrains how evenly peptide is distributed across tablets. It says nothing about how much of each dose crosses the gut wall.
Tjänster The population PK analysis of oral semaglutide puts the absorbed fraction at 0.795% absolute bioavailability (95% CI 0.736–0.864), with mean estimated F of 0.76% in healthy subjects and 0.69% in T2D, plateauing near 1.4% på 120 minutes post-dose fasting (Clinical Pharmacokinetics of Oral Semaglutide, 2021-05-10). At those fractions, the dose-multiplication arithmetic runs to roughly 100 times the parenteral dose for matched systemic exposure, so a small relative swing in absorbed fraction becomes a large absolute swing in exposure.
Formulation choices shift that fraction but do not remove the variability. In the oral semaglutide experience review, 300 mg SNAC was the optimal enhancer load: exposure was higher at 300 mg than at 150 eller 600 mg, och 300 mg is believed to avoid the precipitation seen at higher loads (The Oral Semaglutide Experience, 2023-08-22). The relationship is non-monotonic, which is why dose consistency for oral peptides has to be demonstrated across the enhancer range rather than at a single point.
Nedbrytning och föroreningskontroll: vilket alternativ är lättare att karakterisera?
The oral candidate wins this criterion, and it wins for a structural reason rather than a chemical one: a tablet or capsule is a more tractable analytical object than a sterile injectable, because the sample is homogeneous, stable at bench conditions, and can be sampled unit by unit.
The stability-indicating set that supports the comparison is the same for both routes, but the oral route makes it easier to execute: identity by MS with sequencing or peptide mapping; purity and related substances by RP-HPLC or UPLC; impurity and degradant profiling by LC-MS; assay stated on an explicit gross-versus-net peptide content basis; unit-by-unit content uniformity; dissolution for release performance and formulation comparability; and formal long-term and accelerated stability with forced degradation. The forced-degradation probe set is defined by the ICH Q1A(R2) stress-testing matrix, which is what makes a degradant claim defensible rather than incidental.
Peptidsyntes The injectable control is not the harder characterisation problem in every respect. Its impurity burden is dominated by aggregation, particulates, and sterility or endotoxin considerations, and endotoxin limits are arithmetic, not judgement: the FDA endotoxin limit arithmetic sets the threshold from K/M, 5.0 EU/kg for the intravenous route, with a 0.5 EU/mL worked example. That is a defined number to hit.
The oral route adds degradant pathways the injectable does not have, and the failure record shows what happens when they are not resolved early. In the calcitonin failure analysis, the Phase III oral salmon calcitonin programme failed on insufficient gastric absorption, with plasma concentrations at the limit of detection, compounded by limited bone-tissue availability, receptor distribution in non-skeletal tissues, and fibrilization-driven potency loss. Purity that passes an HPLC threshold is not the same as purity that survives a discriminating biological assay, and that gap is where peptide stability and permeability work has to start.
Vårt fynd: the oral candidate is easier to characterise in the dosage-form sense, and harder in the degradant sense. Both claims have to be made with the same analytical set, or the comparison is not a comparison.
Jämförbarhetsbevis: vad som krävs för att hävda en muntlig kandidat matchar dess injicerbara kontroll
The injectable control wins this category by default. The comparability claim belongs Handla to the oral candidate, and the current evidence base does not discharge it.
The clearest worked example is the Mycapssa label’s single-dose comparison. In it, 20 mg oral octreotide produced systemic exposure (AUC) similar to 0.1 mg subcutaneous octreotide acetate, but peak plasma concentration (Cmax) was 33% lower by the oral route, and time to peak (tmax) anlände till 1.67 till 2.5 hours orally against 0.5 hours subcutaneously. Exposure was dose-proportional across 3 till 40 mg.
Matched AUC with a lower, later peak is not matched pharmacokinetics and pharmacodynamics. Whether the gap matters depends on whether efficacy is driven by total exposure or by peak concentration, and that is a per-drug question, not a route-level one.
The regulatory framing sets the burden. Under FDA’s ANDA versus 505(b)(2) decision framework, an ANDA requires sameness to the reference listed drug in active ingredient, dosage form, route, styrka, conditions of use and labeling, with only justified permitted differences. A 505(b)(2) applicant may rely in part on prior findings but must supply data supporting each difference, typically bioavailability or bridging, food-effect, and clinical or nonclinical data as needed.
Food effect is where that burden bites hardest. The Mycapssa label’s food-effect data record approximately 90% reduction in rate and extent of absorption with food, which is why dosing is tied to a fasting schedule rather than left to the patient.
Där den muntliga vägen vinner, och där den injicerbara kontrollen fortfarande vinner
The oral route wins where the barrier is not the problem. For gastrointestinal targets, the peptide acts where it already is, so the absorbed fraction stops being the deciding metric. Crohn’s disease, ulcerative colitis and gut-localised bacterial infections sit in that group, and the chemically modified classes built for it, double-bridged and cyclic peptides, hold their shape against enzymatic degradation long enough to matter. Non-invasive administration and patient-friendly use follow from the same logic.
The injectable control wins wherever the therapeutic window is narrow, where peak-driven efficacy rather than total exposure drives the response, or where the target is systemic and the absorbed fraction stays below 1%. That last condition is not a design failure, it is the boundary the field keeps running into: systemically acting peptides generally land under 1% oral bioavailability, with much of the reported work sitting in a 0.4 till 1.0% band, as set out in the pharmacokinetic boundaries of oral peptide delivery. Calcitonin is the cautionary case, a systemic oral program that did not clear the bar, examined in the calcitonin failure analysis.
Key Takeaway: Choose oral when the target is local and exposure is not peak-critical. Keep the injectable control when the target is systemic and the absorbed fraction sits below 1%. If neither fits, the honest answer is a different route or a different modality, not a forced oral program.
Kvaliteten och det analytiska arbetsflödet som gör båda jämförelserna rättvisa
A comparability claim is only as good as the analytical package behind it. The same stability-indicating set that characterises an oral candidate is what makes an injectable control a valid control: without a shared stress matrix, the two datasets describe different molecules under different conditions and no comparison holds. The ICH Q1A(R2) stress-testing matrix sets that shared baseline for forced degradation, and the FDA endotoxin limit arithmetic and the USP acceptance-value calculation extend it to safety and dose uniformity, so a reviewer can trace each number to a method rather than a summary.
Vårt fynd: MOL Changes is an integrated organic-chemistry and biology R&D organization producing custom and modified peptides under Class 100 cleanroom conditions with HPLC, MS and sterility testing. That package supports the stability-indicating work an oral peptide development programme needs, and it can be used to characterise an injectable control on the same methods, which is what makes the comparison fair rather than merely parallel.
Vanliga frågor
Är en oral peptid utbytbar med dess injicerbara kontroll?
Not on the strength of a matched AUC alone. The Mycapssa label’s single-dose comparison shows matched overall exposure against the injectable control, yet peak concentration ran about 33% lower and arrived Syntetiska peptider på 1.67 till 2.5 hours rather than 0.5 timmar. Interchangeability turns on what the clinical use depends on: a therapy needing a rapid, high peak is not served by a profile that flattens and delays it.
Kan en oral kandidat jämföras rättvist om dess biotillgänglighet är lägre 1%?
Ja, but only at matched systemic exposure rather than matched administered dose. The PK-boundaries review places current oral peptides in a 0.4 till 1.0% bioavailability band, so the oral arm is dosed 10 till 100 times higher to reach the same circulating levels. That multiplication is an arithmetic consequence of the route, and it is why dose consistency for oral peptides becomes the harder problem. Om
Varför måste orala peptider tas fastande?
Because food does not merely slow absorption, it can remove it. The current fasting requirement across oral peptide formulations reflects a consistent finding that dosing with food drives bioavailability toward zero, and the Mycapssa label’s food-effect data records roughly a 90% reduction in both the rate and the extent of absorption.
Vilka nedbrytningsvägar betyder mest för en oral peptid?
Oxidation, deamidering, hydrolysis and aggregation are the four standard chemical and physical routes, and the ICH Q1A(R2) stress-testing matrix is the conventional probe set for forcing them into view early. An oral candidate carries one pathway its injectable control never meets: gastrointestinal proteolysis, where digestive enzymes attack the peptide before it reaches the absorption site.
Är oral peptidutveckling fortfarande värd att sträva efter?
For specific molecules under specific dosing conditions, the approved record says yes: oral semaglutide reached 0.795% absolute bioavailability in the population PK analysis of oral semaglutide. The counterweight is real. The calcitonin failure analysis documents a programme that did not survive, and the complexity review’s publication-bias caveat means the literature over-reports successes, so the true base rate is not knowable from published work.
Slutsats
The criteria-level verdicts are consistent across the comparison. The injectable control wins on dose consistency and on comparability evidence, because its exposure is measured and its reference standard is defined. The oral candidate wins where the target is local or the therapeutic window is wide, and it is easier to characterise when degradation products are known and assayed. Stability and permeability remain the two criteria where the oral route carries the heavier evidence burden.
That gives the decision rule. Choose oral when the target is local or the window is wide and the evidence package is complete. Choose the injectable control when the window is narrow, efficacy is peak-driven, or the absorbed fraction sits below 1%, the class-wide ceiling described in the PK-boundaries review. Where neither fits, change route or modality rather than force the comparison. Read the Mycapssa label’s single-dose comparison as the benchmark for what matched exposure with a 33% lower Cmax and later tmax actually requires, and treat the complexity review’s publication-bias caveat as a warning against reading the literature as a clean scoreboard. Peptidproduktion
Commercial interest: MOL Changes supplies peptide synthesis and analytical services, so it has a commercial interest in peptide quality standards. This article is technical material for development teams, not medical advice.
If you are weighing an oral candidate, start with a technical feasibility assessment and request the documentation package: analytical data and sterility documentation for the peptide work you are scoping.





